



Digitalis glycosides are among the oldest therapies for heart failure (HF) with reduced ejection fraction, yet their contemporary role remains debated. Clinical data now indicate that the predominant clinical benefits of digitalis appear to derive from autonomic and neurohormonal modulation (enhanced vagal activity, attenuation of sympathetic drive, and suppression of renin–angiotensin–aldosterone activation) rather than from classical positive inotropy. At low serum concentrations, these effects translate into improved rate control, reduced congestion, and fewer decompensations with a lower risk of toxicity, whereas higher “inotropic” levels are associated with proarrhythmia and excess mortality. This review summarises the mechanistic and pharmacokinetic differences between digoxin and digitoxin, appraises evidence from PROVED, RADIANCE and DIG, and integrates emerging outcome data from DIGIT-HF, which showed that low-dose digitoxin added to contemporary guideline-directed therapy reduces the composite of death or HF hospitalisation. Finally, this review also provides valuable insights from a 2025 survey of Portuguese HF specialists into real-world clinical practice regarding digitalis use. With 55 experts responding, the survey highlights a predominant, selective application of digitalis glycosides, primarily after optimization of foundational HF therapies, consistent with guideline recommendations. Perceived benefits focus on rate control and symptom relief, while concerns about toxicity, the need for monitoring, and gaps in modern trial evidence continue to restrict broader adoption. Together, current data support a repositioning of digitalis as a low-dose, concentration-guided, neurohormonal modulator and rate-control agent for carefully selected patients with HF with reduced ejection fraction, an approach that ongoing and future trials should further refine.
Apesar de os digitálicos serem uma das terapêuticas mais antigas para a insuficiência cardíaca (IC) com fração de ejeção reduzida, o seu papel na prática clínica atual continua a ser objeto de debate. Dados clínicos recentes demonstram que os benefícios clínicos resultam predominantemente da modulação autonómica e neurohormonal, através do aumento da atividade vagal, atenuação da estimulação simpática e supressão da ativação do sistema renina-angiotensina-aldosterona, em detrimento do efeito inotrópico clássico. A concentrações séricas baixas, estes efeitos promovem melhor controlo da frequência cardíaca, redução da congestão e menor incidência de eventos descompensadores de IC, com risco reduzido de toxicidade, ao passo que níveis elevados se associam a risco arrítmico e de mortalidade excessiva. Esta revisão sintetiza as diferenças mecanísticas e farmacocinéticas entre digoxina e a digitoxina, avalia a evidência dos ensaios PROVED, RADIANCE e DIG e integra dados recentes do DIGIT-HF, que evidenciou redução do risco composto de morte ou internamento por IC com digitoxina, sob terapêutica contemporânea de IC. Adicionalmente, apresenta o contributo de 55 especialistas portugueses em IC que responderam a um inquérito sobre a utilização contemporânea de Digitálicos na prática clínica. Os benefícios mais valorizados centram-se no controlo da frequência cardíaca e alívio sintomático, enquanto as preocupações com toxicidade, monitorização e lacunas na evidência de ensaios modernos limitam uma utilização generalizada. Em síntese, os dados atuais favorecem o reposicionamento dos Digitálicos como moduladores neurohormonais, administrados em doses baixas em doentes selecionados com IC com fração de ejeção reduzida. Esta estratégia requer validação em futuros ensaios clínicos.
Digitalis glycosides, derived from the foxglove plant (Digitalis purpurea), have been used for the treatment of “dropsy” and related syndromes for several centuries, long before the pathophysiology of HF was understood. William Withering's 1785 monograph provided the first systematic description of their use in what we would now recognise as chronic HF, detailing dose–response relationships, therapeutic effects, and signs of toxicity with remarkable clinical precision.1 Through the 19th and much of the 20th century, digitalis became a cornerstone of cardiac practice, used both to relieve congestion and to control supraventricular tachyarrhythmias, and the concept of “digitalisation” was deeply woven into bedside management and the evolving understanding of myocardial function.2
Despite being embedded in the historical and conceptual development of HF therapy, the advent of diuretics, vasodilators and, more recently, neurohormonal modulation, together with the narrow therapeutic window of digitalis and concerns regarding severe toxicity, have reduced its centrality in contemporary care.3,4 Additionally, the role of digitalis glycosides for current HF with reduced ejection fraction therapy is uncertain, as there are only a few randomized clinical trials with digoxin, all performed before current standard HF with reduced ejection fraction medical treatment was established. The paradigm may be shifting, however, with renewed interest in these inexpensive drugs and recent trials such as DIGIT-HF, in which digitoxin added to guideline-directed therapy improved outcomes in a contemporary HF with reduced ejection fraction population.5 Against this backdrop, this article aims to review the mechanisms of action of digitalis glycosides (digoxin and digitoxin), summarise the current evidence base, examine international guideline recommendations and their translation into clinical practice, and present the perspectives of national HF experts based on a dedicated survey.
Beyond inotropy: mechanistic and pharmacokinetic foundationsDigitalis glycosides act primarily by inhibiting the membrane-bound Na+/K+-ATPase. This pump normally extrudes Na+ in exchange for K+, and its inhibition increases intracellular Na+, which in turn reduces the activity of the Na+/Ca2+ exchanger. The resulting rise in intracellular Ca2+ and enhanced filling of the sarcoplasmic reticulum Ca2+ stores augment Ca2+ release with each heartbeat, producing a positive inotropic effect and increased stroke volume. Importantly, this inotropic action typically requires higher doses and serum concentrations, bringing the drug closer to its toxic range and increasing the risk of proarrhythmia and other adverse effects.2
Electrophysiologically, digitalis glycosides influence the sinoatrial and atrioventricular nodes by altering diastolic potentials and depolarisation kinetics, but in clinical practice, the dominant effects on heart rate and AV conduction are largely indirect, mediated via the autonomic nervous system. At lower therapeutic doses, they enhance vagal tone and suppress sympathetic activity, leading to reduced sinus rate and slowed AV nodal conduction, which are key to rate control in Atrial Fibrillation (AF). At higher doses, however, excess intracellular Ca2+ and increased sympathetic drive can facilitate delayed after depolarisations, ectopy, and conduction block, predisposing to complex arrhythmias.2
At low doses, digitalis increases carotid baroreceptor sensitivity and activates central vagal nuclei, which together blunt the excessive sympathetic outflow characteristic of HF with reduced ejection fraction. This sympathoinhibition is accompanied by downregulation of renin release from the kidney and attenuation of renin–angiotensin–aldosterone system activation, contributing to reduced vasoconstriction, afterload, and sodium retention. In parallel, inhibition of Na+/K+-ATPase in renal tubular cells may modestly reduce tubular Na+ reabsorption and support natriuresis.2 These neurohormonal and renal actions occur at serum concentrations lower than those required for a strong inotropic response and are associated with a more favourable safety profile.
It is now clear that for patients with HF, the principal clinical benefits of digitalis glycosides derive primarily from their autonomic and neurohormonal effects, such as enhanced vagal tone, suppression of sympathetic activity, and neurohormonal modulation, rather than from their classical positive inotropic action.2,6
Digoxin and digitoxin share the same basic mechanism but differ markedly in their pharmacokinetics, with important clinical implications. Digoxin contains digoxigenin, which has a hydroxyl (–OH) group at the C-12 position on the steroid nucleus. Digitoxin contains digitoxigenin, which lacks this C-12 hydroxyl group.7 Digoxin has moderate oral bioavailability, relatively low protein binding, a large volume of distribution with extensive tissue uptake, and is cleared predominantly unchanged by the kidneys, with a plasma half-life of ∼1.5–2 days that is markedly prolonged in renal dysfunction. By contrast, digitoxin is highly protein bound, more lipophilic, and cleared mainly by hepatic metabolism with enterohepatic recirculation, giving it a much longer half-life (6–7 days) and making its elimination less dependent on renal function. These differences mean that digoxin reaches steady state more quickly and requires dose adjustment and monitoring in chronic kidney disease. In contrast, digitoxin has a slower onset and offset of action, a greater risk of accumulation with interacting drugs that affect hepatic metabolism or protein binding but may be easier to use in renal impairment.8
Navigating the narrow window: monitoring, targets, and toxicity of digitalis in heart failureSerum concentrations of digitalis glycosides exhibit considerable interindividual variability that is not fully explained by age, body weight, dose, or renal function, and require monitoring. For HF, therapeutic serum concentrations of digoxin are generally 0.5–0.9 ng/mL,9 and for digitoxin roughly 8–18 ng/mL,5 with blood sampling performed from 6 to 24 hours after the last dose to allow distribution equilibrium. Current European guidelines suggest that digoxin levels should be checked aiming for a serum digoxin concentration <1.2 ng/mL.10
Within these ranges, adverse effects and toxicity are uncommon; toxic manifestations usually occur with digoxin levels >2.0 ng/mL and digitoxin levels >30 ng/mL and include a broad spectrum of brady- and tachyarrhythmias (the most frequent manifestation), as well as gastrointestinal symptoms (nausea, vomiting, diarrhoea, anorexia) and neurological/visual disturbances (confusion, hallucinations, colour-vision changes). Toxicity risk is strongly modulated by comorbidities and concomitant drugs: hypokalaemia, hypomagnesaemia, hypercalcaemia, hypothyroidism, and interacting medications can precipitate toxicity.
In addition to serum digoxin concentration, serum potassium is a critical determinant of toxicity, as hypokalaemia sensitises the myocardium to a given digoxin level and markedly increases the risk of ventricular and supraventricular arrhythmias; consequently, careful monitoring and prompt correction of electrolyte disturbances, particularly potassium, is essential during treatment with cardiac glycosides.11
Dose reductions are often required for digoxin in renal dysfunction due to its renal clearance, whereas digitoxin, cleared mainly by the liver, remains largely unaffected; in both cases, doses should typically be reduced in older patients due to lower muscle mass and smaller volume of distribution.2
Clinical evidence: lessons from old and new trialsWithdrawal trials: early clues from PROVED and RADIANCEThe first modern randomized evidence for digoxin in HF with reduced ejection fraction comes from the withdrawal studies PROVED and RADIANCE, both conducted in patients with stable, mild–moderate systolic HF in sinus rhythm who were already on chronic digoxin.
In the PROVED, published in 1993, patients receiving digoxin and diuretics were randomized to continue digoxin or switch to placebo; withdrawal led to a significant reduction in exercise capacity at 12 weeks (median change in exercise time −96 sec) and a higher rate of predefined treatment failure.12
The RADIANCE, also published in 1993, extended this to patients also treated with ACE inhibitors: stopping digoxin, compared with continuation, resulted in deterioration of maximal and submaximal exercise tolerance, worsening NYHA class and quality of life, reduced left ventricular ejection fraction, and increases in heart rate and body weight at 12 weeks.13
The DIG Study: neutral on mortality but reducing heart failure hospitalizationsFollowing the small withdrawal studies PROVED and RADIANCE, the pivotal DIG trial evaluated the effect of chronic digoxin therapy on hard outcomes in a large, contemporary-for-its-time HF with reduced ejection fraction population. DIG enrolled about 6800 patients with NYHA class I–IV symptoms, left ventricular ejection fraction <45%, and sinus rhythm, all receiving background therapy with an ACE inhibitor and diuretics but not β-blockers, as pivotal β-blocker trials had not yet been reported. Patients with AF were excluded from the trial, as including them was deemed unethical at the time of study design, given that digoxin was then the only approved therapy for ventricular rate control in this population.
Patients were randomized to digoxin or placebo and followed for overall mortality as the primary endpoint. Digoxin had a neutral effect on all-cause mortality and on predefined secondary endpoints of cardiovascular mortality and death due to worsening HF. In the prespecified health-related quality-of-life substudy of the DIG trial (589 patients), only a transient improvement in perceived health at 4 months was observed in the digoxin arm. At 12 months, there were no statistically significant differences between groups in any quality-of-life domain, indicating that digoxin did not improve health-related quality of life.14
In contrast, it significantly reduced the predefined secondary endpoint of cardiovascular hospitalizations, driven by an approximate 28% reduction in hospitalizations for worsening HF. Together, these findings positioned digoxin as a drug that reduced HF-related admissions without conferring either benefit or harm on survival in a pre-β-blocker era HF with reduced ejection fraction population in sinus rhythm.15
Packer's accompanying editorial emphasized the modest overall clinical impact: “Digoxin had no effect on mortality but reduced the risk of any hospitalization by 8 percent. This reduction, though significant, is so small that physicians would avoid only 9 hospitalizations by treating 1000 patients with digoxin for one year”.16
Reinterpreting the DIG Study: subgroups and serum valuesSince the main DIG report, multiple post hoc and ancillary analyses have refined our understanding of which HF with reduced ejection fraction patients are most likely to benefit from digoxin. A prespecified subgroup analysis identified “high-risk” patients (those with NYHA III–IV symptoms, left ventricular ejection fraction <25%, or cardiothoracic ratio >55%) in whom digoxin significantly reduced the composite of HF death or hospitalization (HRs ∼0.61–0.65 over the first two years).17 The ancillary DIG trial in patients with diastolic HF (HFpEF) showed no effect of digoxin on mortality or all-cause hospitalization, with only a non-significant trend toward fewer HF hospitalizations.18 When the main and ancillary DIG populations were analysed across the full left ventricular ejection fraction spectrum, benefit on the composite of cardiovascular death and HF hospitalization was concentrated below a left ventricular ejection fraction of roughly 35%, with little or no effect in HFmrEF and HFpEF.19 Regarding serum digoxin concentration (SDC), a series of analyses then showed a near-linear relationship between SDC and risk: levels in the range of about 0.5–0.9 ng/mL were associated with reduced mortality and HF admissions, concentrations around 0.9–1.2 ng/mL appeared neutral, and higher levels (≥1.2 ng/mL) were linked to excess mortality, particularly in women and in older patients who had impaired renal function, low body mass, or were on high daily doses (≥0.25 mg) and intensive diuretic therapy. Additionally, early sex-specific analyses suggested harm in women, but later work indicated that this was largely driven by higher achieved SDCs rather than a fundamentally different biological response. Together, these data support a strategy of low-dose digoxin, targeting SDCs around 0.5–0.9 ng/mL, starting at 0.125 mg or even 0.0625 mg daily in patients at risk of high levels, with serum concentrations checked after about 4 weeks to guide titration, and reserving treatment primarily for patients with high-risk HF with reduced ejection fraction.20–22
AF and digitalis indications: lessons in bias from observational studiesIn patients with HF with reduced ejection fraction and AF, digitalis glycosides are primarily used for ventricular rate control, particularly when β-blockers are contraindicated, not tolerated, or insufficient. Guidelines generally support digoxin as a rate-control option in this setting but emphasize careful dosing because observational and post hoc analyses in AF cohorts suggest excess mortality at serum levels ≥1.0 ng/mL, whereas levels <0.8 ng/mL appear associated with the lowest mortality in HF. In patients with HF and AF, starting digoxin is consistently linked to fewer HF readmissions, but not to a reduction in all-cause mortality.23,24
More recently, randomized data from RATE-AF (less than 20% of the study population with reduced ejection fraction) showed that digoxin, compared with β-blockers, improved left ventricular ejection fraction, natriuretic peptide levels, and NYHA class in AF patients with HF symptoms.24,25 Still, large observational studies and meta-analyses in AF populations (many with coexisting HF) repeatedly report a moderate increase in all-cause and cardiovascular mortality with digoxin compared with β-blockers, so in contemporary practice digitalis glycosides are best viewed as second-line or adjunctive agents for rate control and symptom relief, used at low doses with strict attention to serum concentrations, renal function, and drug interactions.26,27
Interpretation of digoxin's effect in HF and AF is heavily complicated by prescription bias. Numerous observational studies, registry analyses, and secondary analyses of trials have reported everything from apparent excess mortality to neutrality or even benefit with digoxin, often using overlapping datasets but reaching different conclusions.28 The AFFIRM trial provides a paradigmatic example, in which different groups analysing the same database with distinct statistical approaches reported conflicting effects of digoxin on mortality. These divergent findings highlight the substantial risk of residual confounding and methodological bias in non-randomised or post-hoc evaluations of digitalis, and reinforce the need for cautious interpretation of such data.29–31
This inconsistency largely reflects the fact that digoxin is typically prescribed when patients deteriorate, so crude and even adjusted comparisons systematically disadvantage the digoxin group. This was illustrated in further analyses of the DIG trial from sinus rhythm patients, where randomized allocation to digoxin reduced HF hospitalizations without affecting mortality, regardless of prior digoxin use, whereas non-randomized pretrial digoxin exposure was associated with higher mortality and hospitalization even in patients later assigned to placebo.32
Intravenous digoxin remains an option for acute rate control in hemodynamically stable patients with AF complicating HF, particularly when beta-blockers or calcium channel blockers are contraindicated. However, its relatively slow onset of action (typically 1–2 hours for peak effect) limits its utility in rapid ventricular response scenarios, and careful patient selection is required to avoid exacerbating hypotension or conduction abnormalities.27
Modern trials: DIGIT-HF and the DECISION StudyThese limitations of non-randomized data and the clear evidence of prescription bias underline the need for additional, contemporary randomized evidence to clarify the true effect of cardiac glycosides in HF. Existing data leave open two key questions: whether low-dose digoxin, titrated to “neurohormonal” rather than inotropic serum levels, can improve hard outcomes when added to full guideline-directed therapy, and how best to position digoxin across the spectrum of reduced and mildly reduced left ventricular ejection fraction and coexisting AF. This is the rationale for the DECISION trial, a modern, double-blind, placebo-controlled outcome study in patients with chronic HF and left ventricular ejection fraction <50%, in sinus rhythm or AF, already receiving contemporary HF with reduced ejection fraction therapy. DECISION specifically tests a low-dose, concentration-guided digoxin strategy targeting serum levels of 0.5–0.9 ng/mL, with a primary composite endpoint of cardiovascular mortality and total HF hospitalizations/urgent HF visits, aiming to determine whether carefully titrated digoxin can deliver incremental prognostic benefit beyond current standard care.33
In parallel with this ongoing work with digoxin, the DIGIT-HF trial provides the first contemporary evidence that a cardiac glycoside can improve hard outcomes on top of full guideline-directed therapy. In patients with chronic HF with reduced ejection fraction on modern background treatment, low-dose digitoxin reduced the composite of all-cause death or first hospitalization for worsening HF over a median 36-month follow-up (39.5% vs 44.1% with placebo; HR 0.82, 95% CI 0.69–0.98), with numerically lower rates of both all-cause mortality and first HF hospitalization, although these individual components did not reach statistical significance. The benefit was consistent across key prespecified subgroups, including patients on contemporary quadruple therapy, those with AF, renal impairment, and older age, with no signal of harm in any subgroup. Digitoxin was generally well tolerated, with a modest excess of serious adverse events (4.7% vs 2.8%) but no new safety concerns, and a simple, risk-adapted dosing scheme (0.07 mg daily, reduced to 0.05 mg in patients at higher risk of elevated levels) was effective in maintaining low serum concentrations and minimizing toxicity. Overall, DIGIT-HF suggests that carefully dosed digitoxin can confer incremental reduction in the risk of death or HF hospitalization in selected HF with reduced ejection fraction patients, even in the era of comprehensive neurohormonal and SGLT2 inhibitor therapy.5
However, digitoxin is not commercially available in Portugal, limiting the direct applicability of DIGIT-HF findings to national clinical practice. Portuguese clinicians rely exclusively on digoxin, whose distinct pharmacokinetic profile (shorter half-life, predominantly renal clearance) requires specific monitoring, particularly in patients with renal impairment. The DECISION trial will help fill this important knowledge gap regarding digoxin's role in contemporary heart failure therapy.33
Guideline positioning: a drug in search of its new roleContemporary guidelines give digitalis a limited, add-on role in HF, and these recommendations all predate DIGIT-HF. The 2021 ESC HF guideline states that in HF with reduced ejection fraction and sinus rhythm, digoxin may be considered in patients already treated with guideline-directed therapy (ACEi/ARB/ARNI, β-blocker, MRA, SGLT2 inhibitor, device when indicated) to reduce HF hospitalizations (Class IIb), while it is not recommended in HFmrEF or HFpEF.10 In patients with HF and AF, ESC guidance positions digoxin as a rate-control drug: β-blockers are first-line, but digitalis is recommended or may be added when rate control is insufficient or β-blockers are contraindicated, both for chronic rate control (NYHA I–III) and for rapid ventricular rate control in decompensated/NYHA IV or acute HF (often intravenously), with target rate guided by symptoms, left ventricular ejection fraction and blood pressure.27 Similarly, the 2022 AHA/ACC/HFSA HF guideline states that in symptomatic HF with reduced ejection fraction despite optimal therapy or when such therapy is not fully tolerated, digoxin might be considered to reduce HF hospitalizations (Class IIb), without any proven mortality benefit, and notes its role as an adjunctive agent for ventricular rate control in AF when β-blockers or non-dihydropyridine calcium-channel blockers alone are inadequate or unsuitable.34
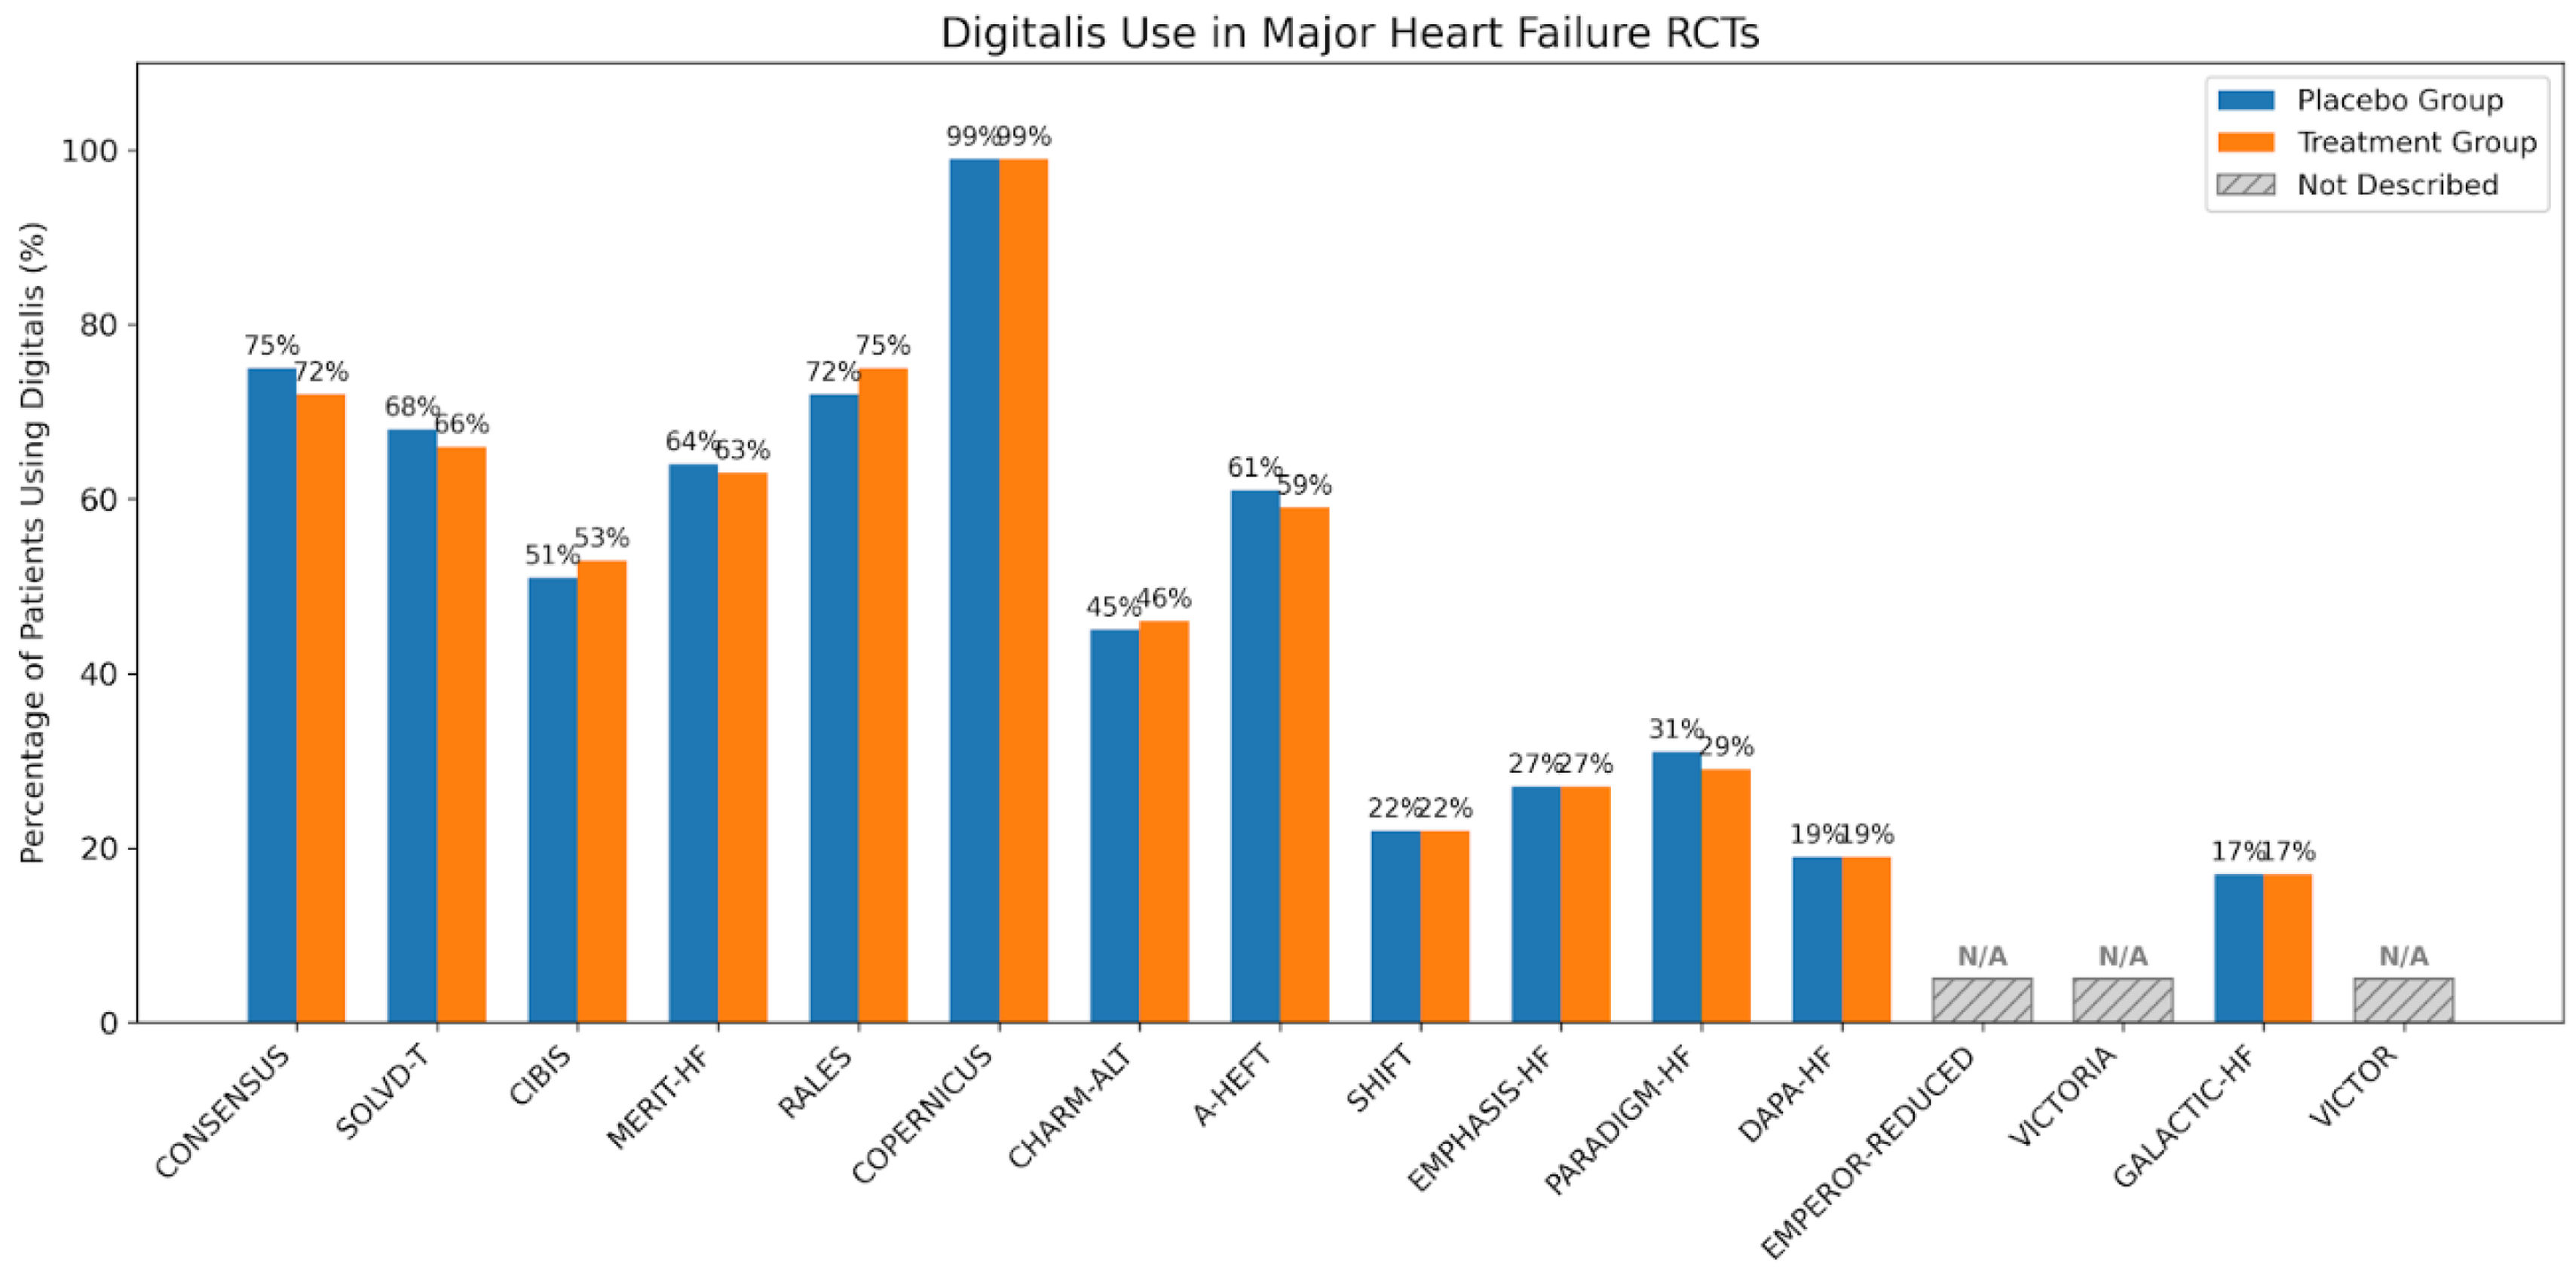
From routine to rarity: the declining use of digitalis in heart failure studies over the last 20 yearsAcross landmark HF trials (Figure 1), the proportion of patients receiving digitalis varied widely. In several early trials such as CONSENSUS, SOLVD-T, MERIT-HF and RALES, more than half of patients were on digitalis, reflecting its status as part of standard care at the time.35–38 In fact, we may argue that the evidence supporting β-blocker trials in HF with reduced ejection fraction, is derived from trials in which the majority of patients were also receiving digoxin, whose positive inotropic effect may counterbalance the potential acute negative effects of β-blockers, so it can be questioned whether the same magnitude of benefit applies to today's populations, in which Digoxin use has fallen dramatically.37,39,40

In more recent trials, the use of digitalis declined substantially, with rates around 20–30% in studies like SHIFT, EMPHASIS-HF, PARADIGM-HF, DAPA-HF and GALACTIC-HF, and in some very recent programmes (EMPEROR-Reduced, VICTORIA, VICTOR) digitalis use was not even reported, suggesting it was either rare or not considered a key background therapy.41–48Figure 1 illustrates a progressive de-emphasis of digitalis in HF with reduced ejection fraction trials over time, despite its persistent use in a minority of patients.
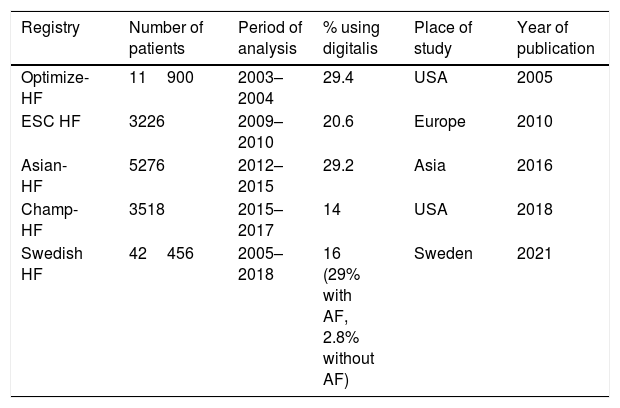
A similar conclusion can be drawn from contemporary HF registries in Table 1, where use of cardiac glycosides among patients has declined consistently over time, reflecting changes in guidelines, the introduction of new therapies, and increasing safety concerns. More recent cohorts, including Champ-HF and the Swedish Heart Failure Registry, show substantially lower overall use, around 14–20%, with higher rates confined to patients with concomitant AF. Taken together, these data suggest that digitalis has progressively shifted from a broadly used background therapy to a more selective option reserved for specific clinical scenarios, particularly rate control in AF.49–53
Percentage of patients using digitalis in registries in heart failure with reduced ejection fraction.
| Registry | Number of patients | Period of analysis | % using digitalis | Place of study | Year of publication |
|---|---|---|---|---|---|
| Optimize-HF | 11900 | 2003–2004 | 29.4 | USA | 2005 |
| ESC HF | 3226 | 2009–2010 | 20.6 | Europe | 2010 |
| Asian-HF | 5276 | 2012–2015 | 29.2 | Asia | 2016 |
| Champ-HF | 3518 | 2015–2017 | 14 | USA | 2018 |
| Swedish HF | 42456 | 2005–2018 | 16 (29% with AF, 2.8% without AF) | Sweden | 2021 |
To better understand how Portuguese HF specialists position the use of cardiac glycosides in 2025, an online survey with 11 structured questions was distributed to assess their use in HF with reduced ejection fraction. Heads of HF services across Portugal were contacted and encouraged to disseminate the survey to their teams for individual anonymous responses.
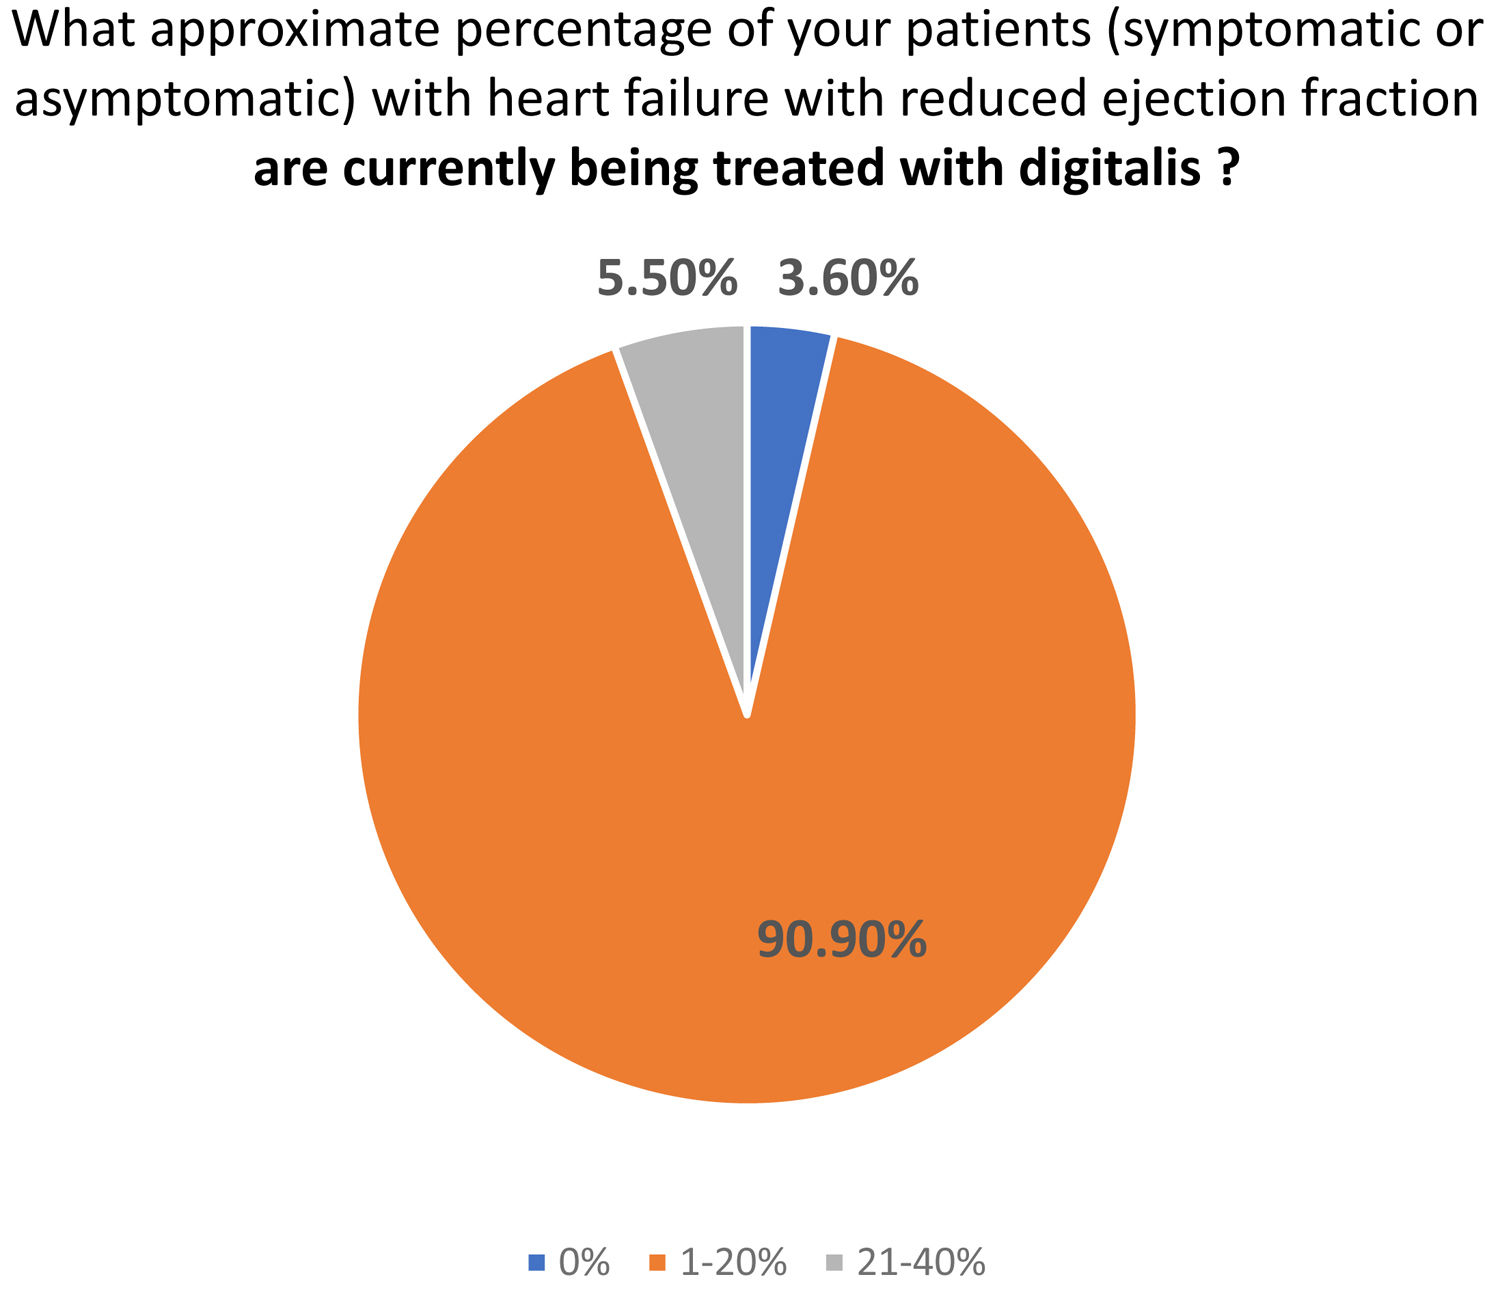
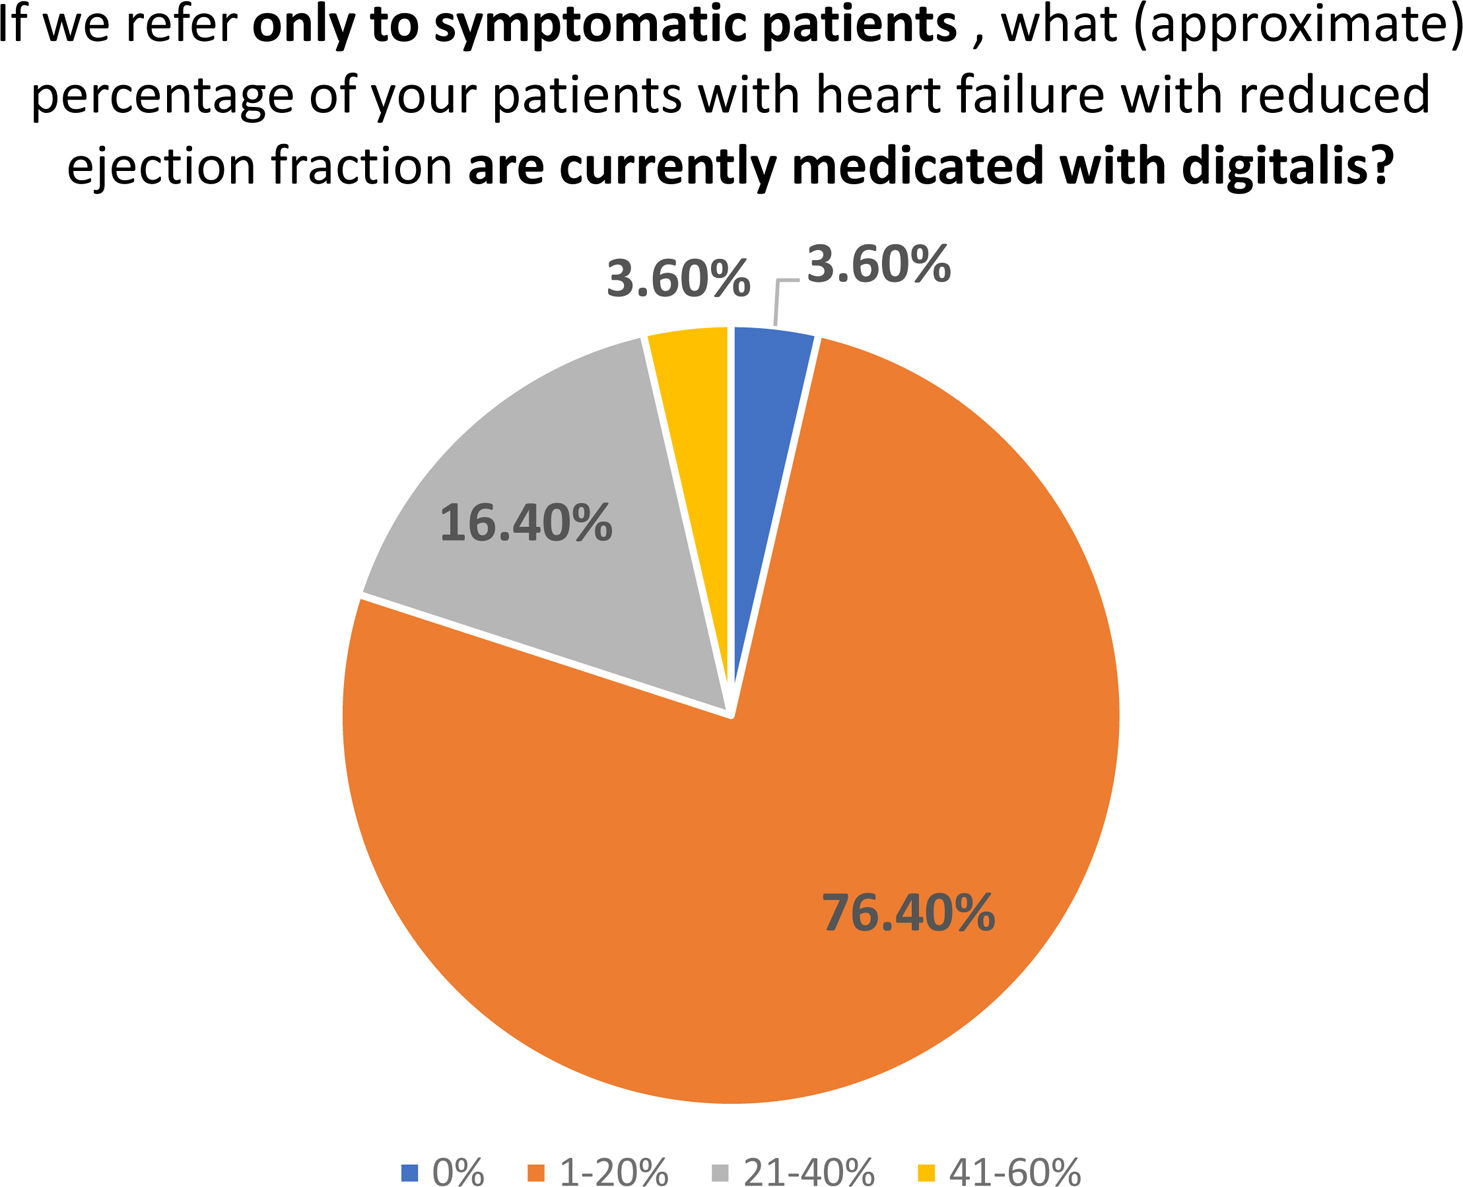
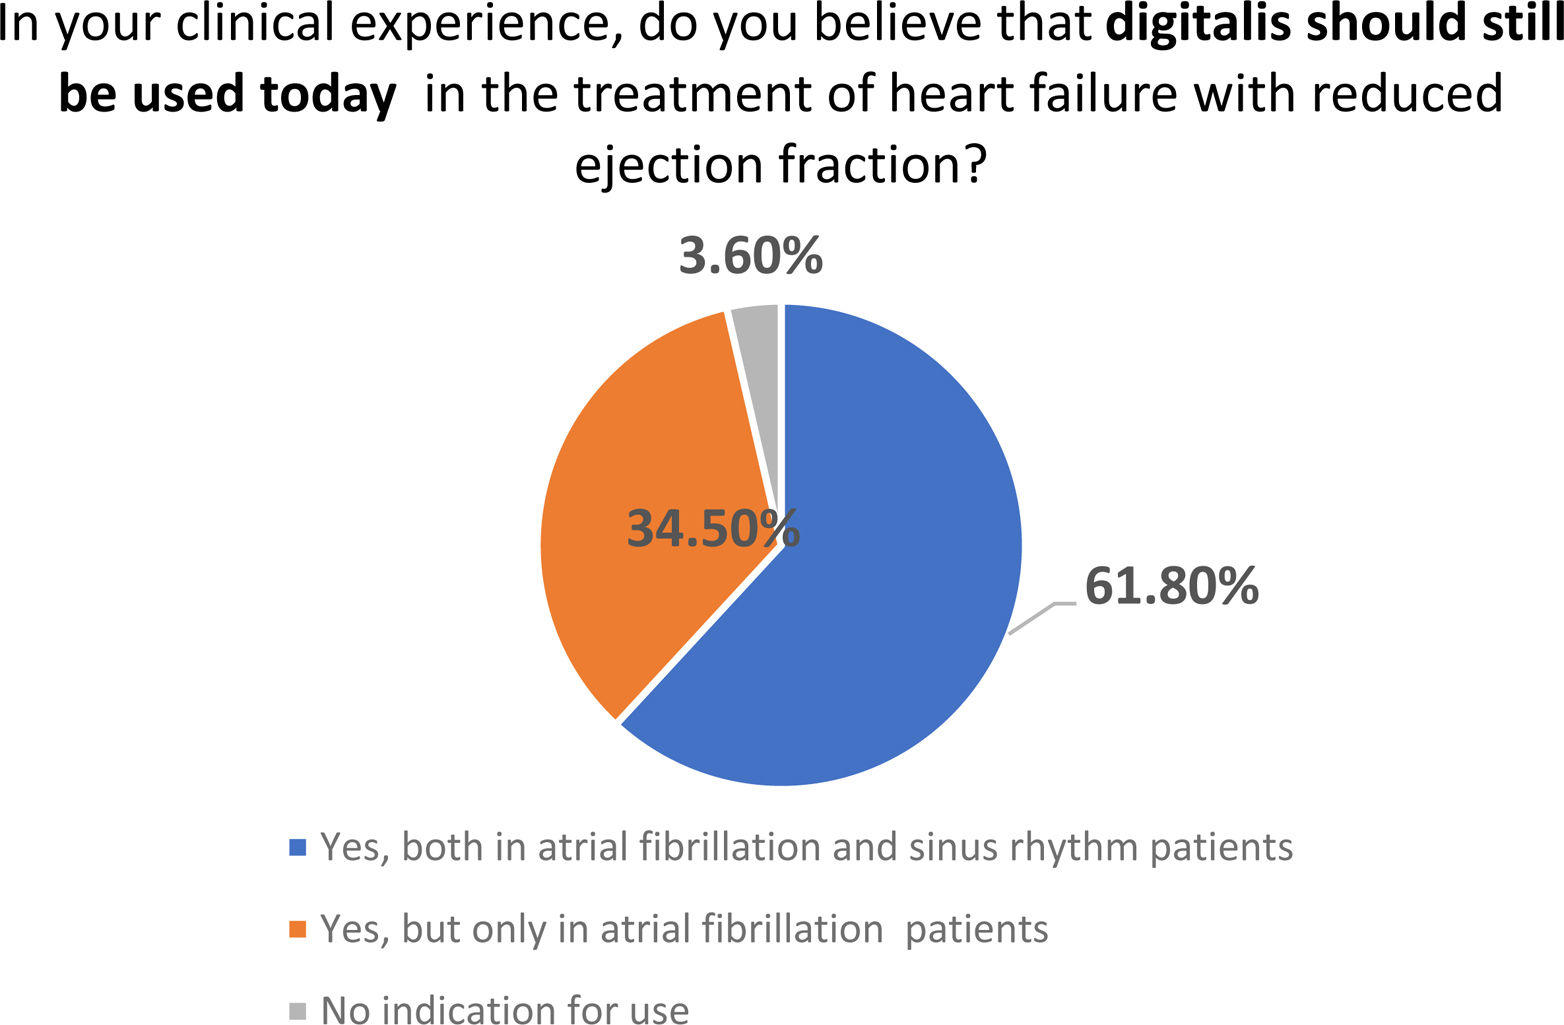
The survey was completed by 55 national specialists (Figures 2–11). Only 3.6% reported never using cardiac glycosides, with more than 90% reporting using them in 1–20% of their HF with reduced ejection fraction patients (Figure 2), a proportion that is broadly consistent with contemporary clinical trials and registries. However, 34.5% of the experts reserved them exclusively for those with concomitant AF, meaning that only 61.8% are still using Digitalis in sinus rhythm patients (Figure 4).


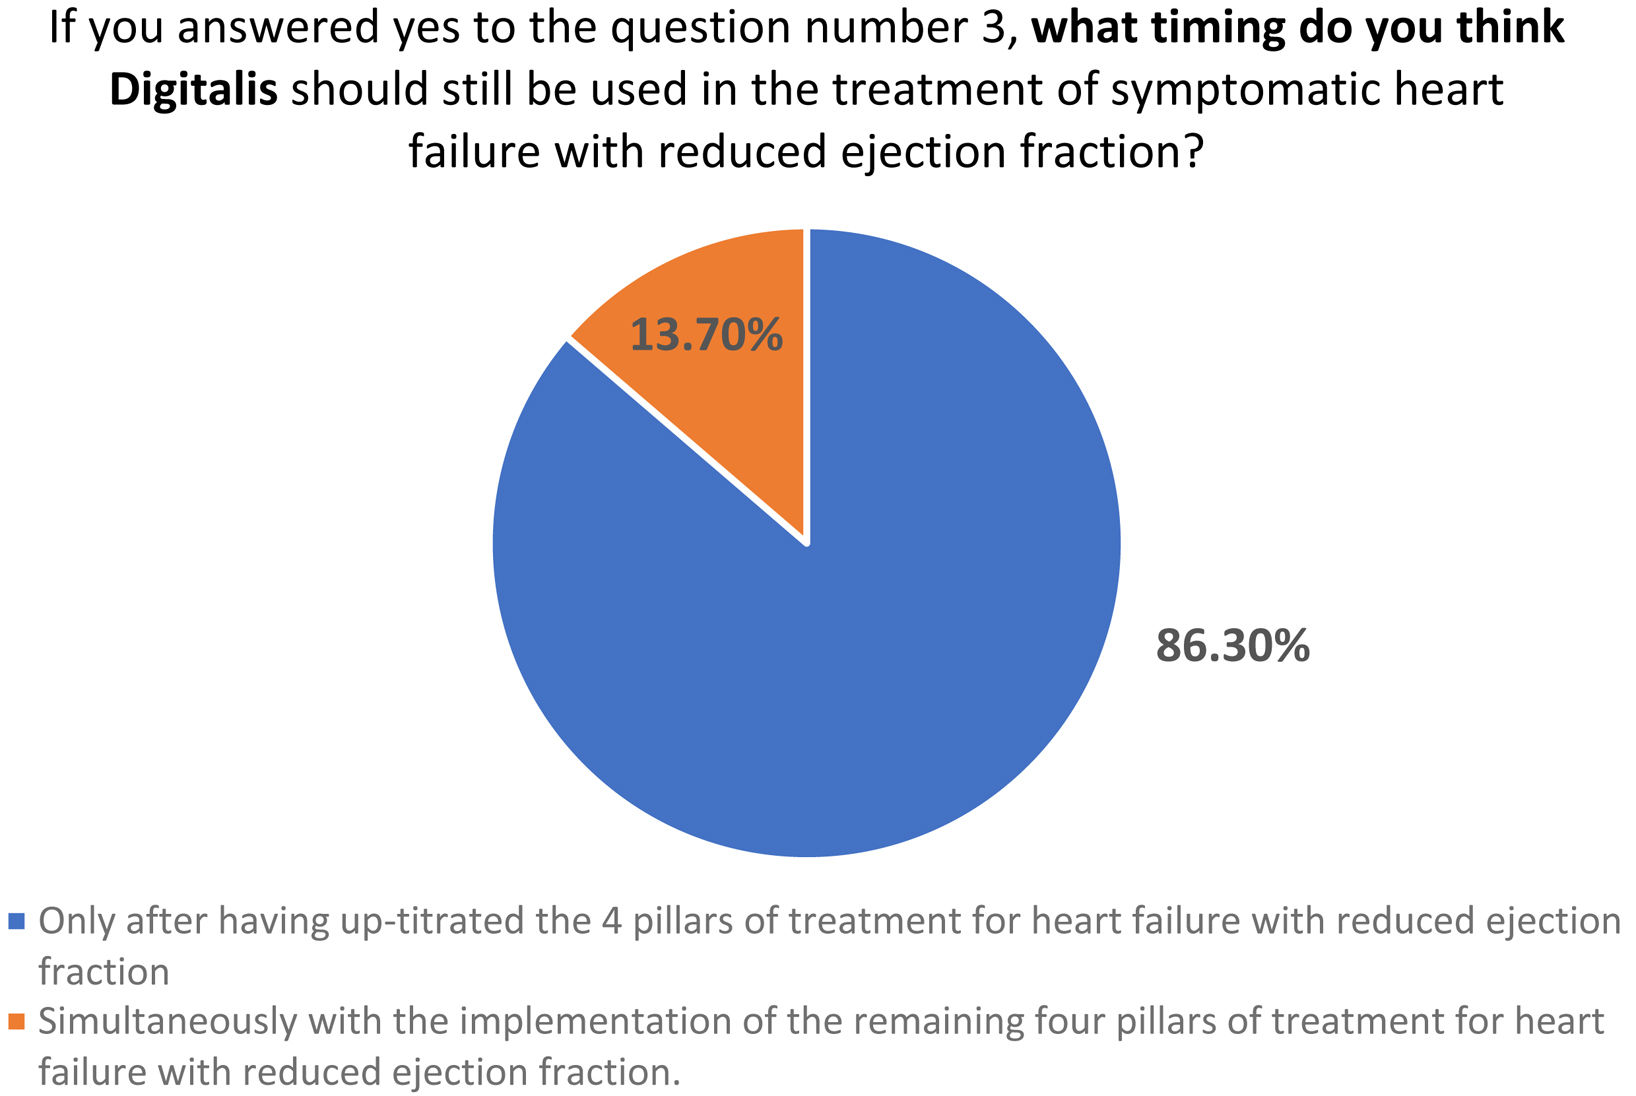
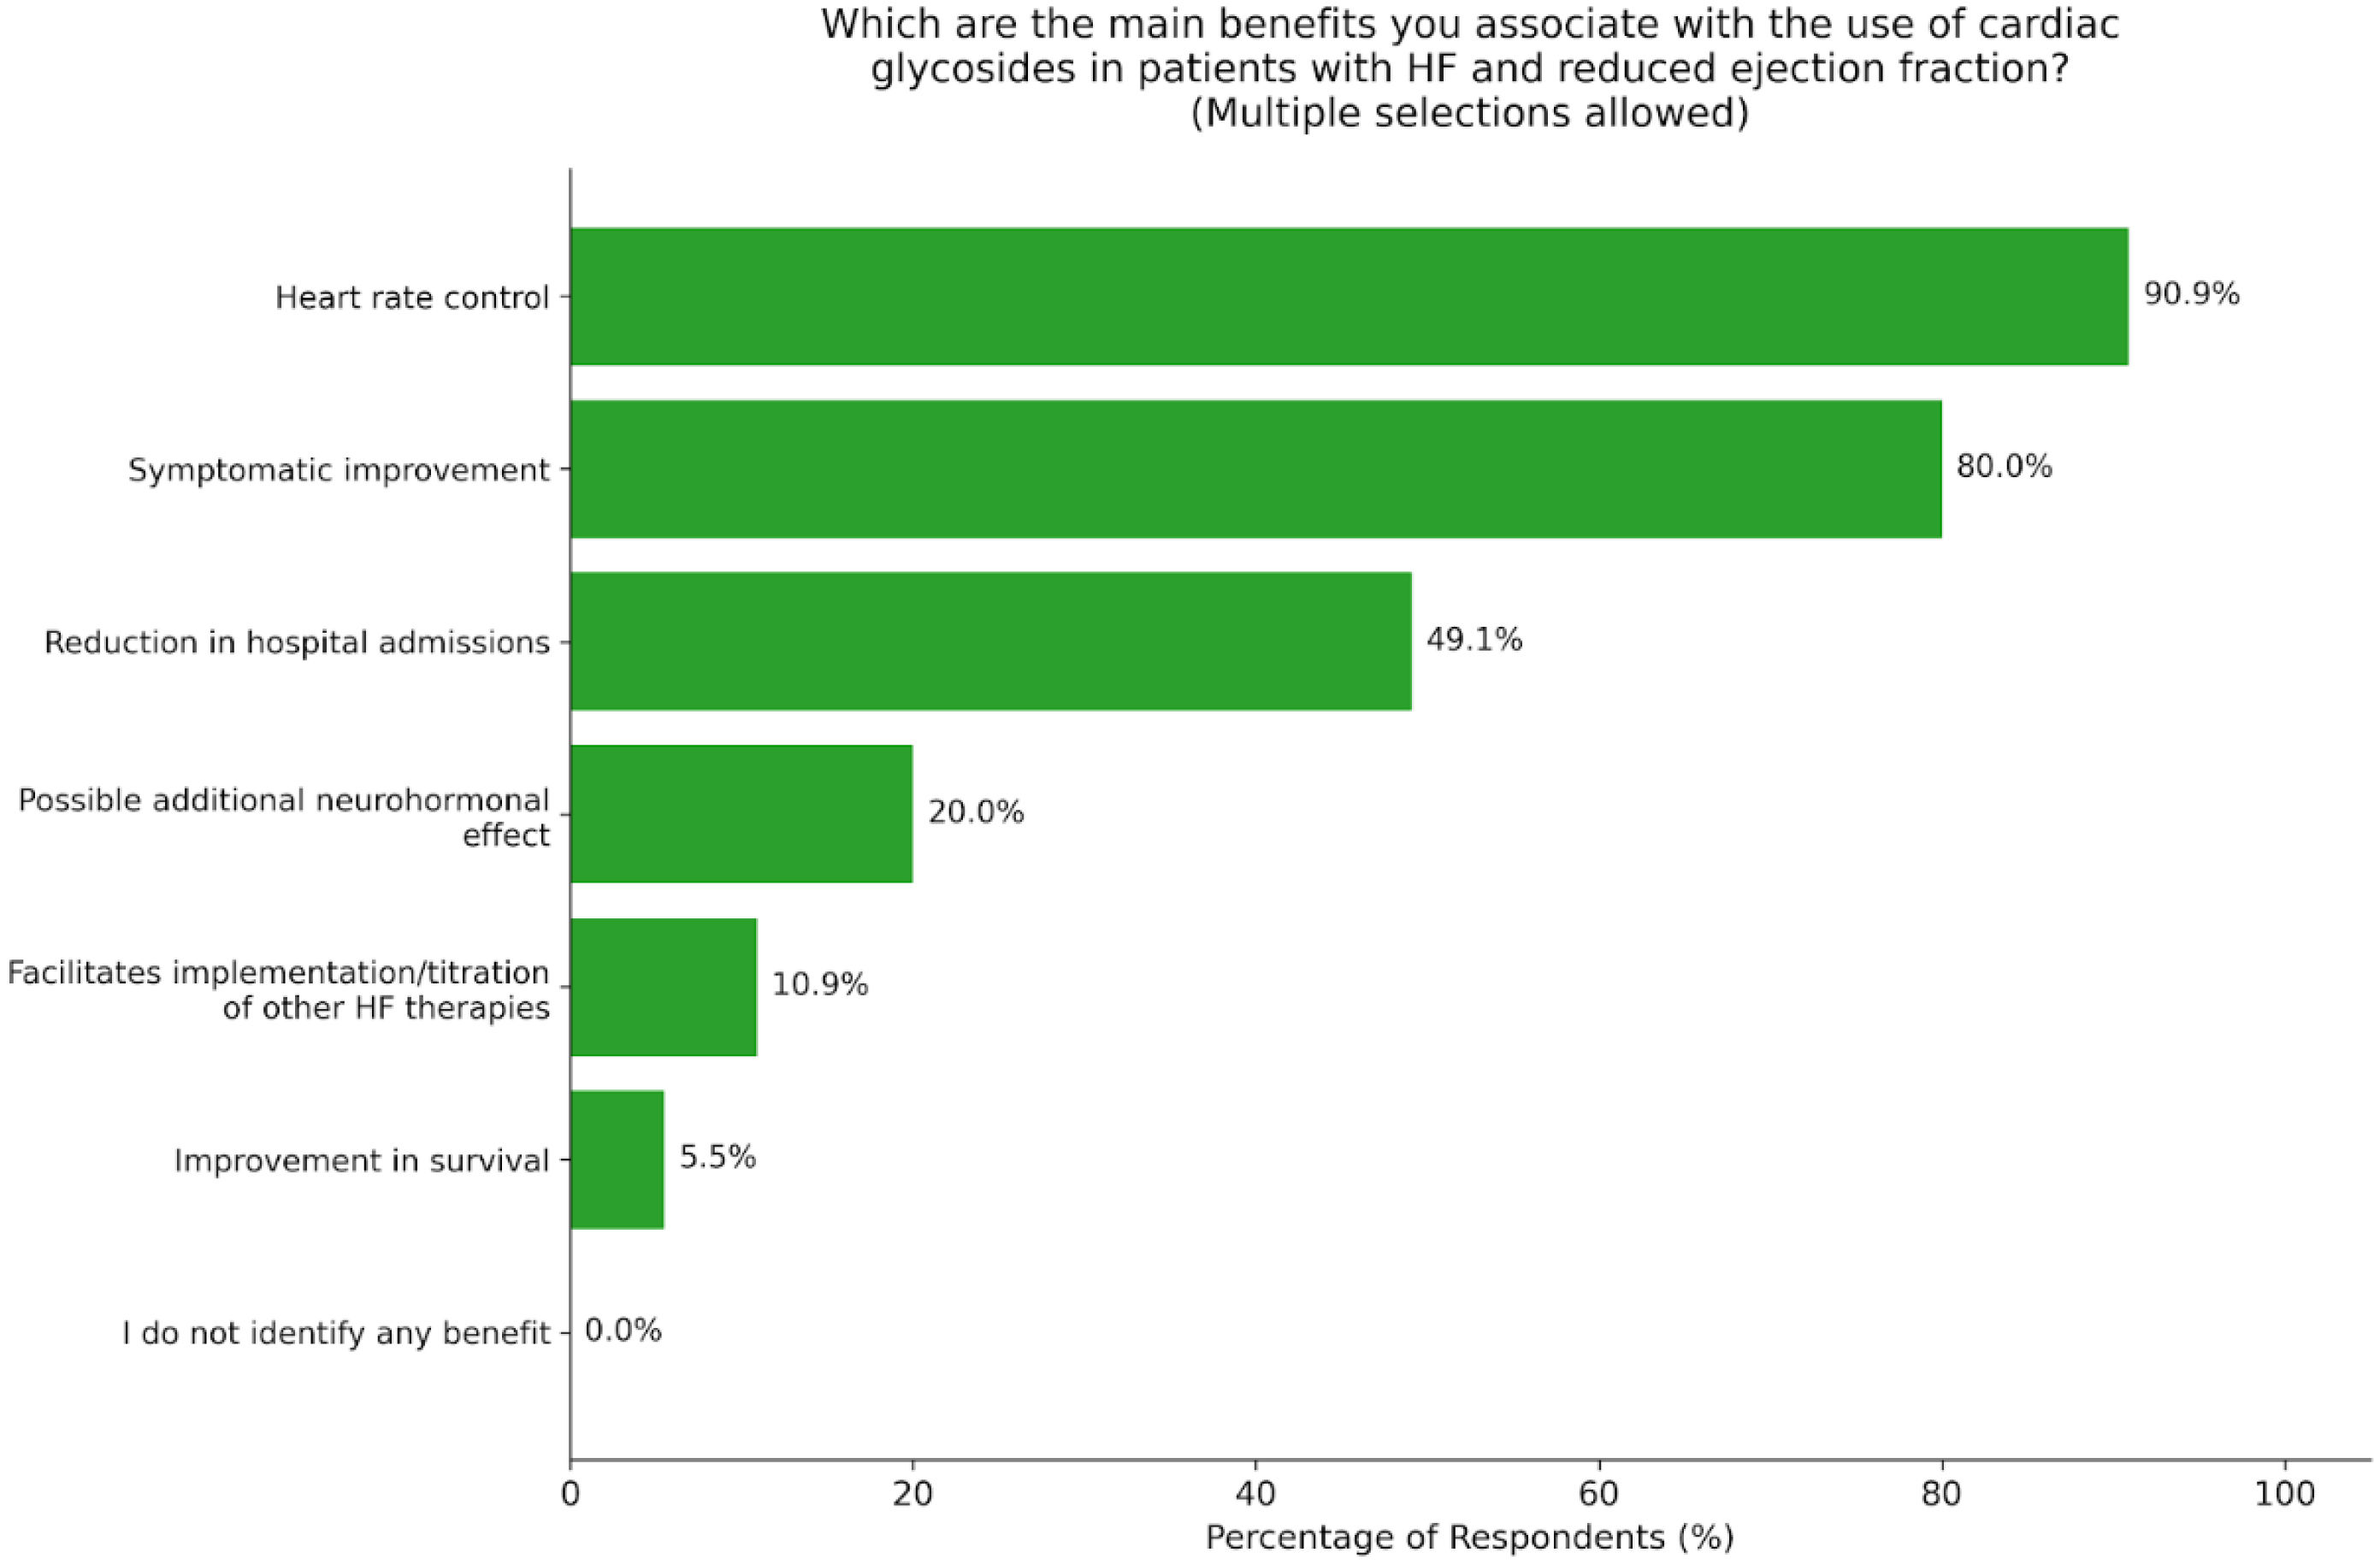
The results indicate that most specialists (86.3%, Figure 5) initiate cardiac glycoside therapy only after optimization of the four main Class I HF treatments (ARNI/ACEi/ARB, β-blockers, MRA, SGLT2i), reflecting current guideline recommendations to prioritize these therapies before introducing digitalis. Among the benefits associated with cardiac glycoside use (Figure 6), heart rate control (90.9%) and symptomatic improvement (80%) are most frequently recognized. Nearly half of the respondents (49.1%) also acknowledge a role in reducing hospital admissions, consistent with evidence supporting its use to stabilize clinical status and prevent decompensation. Although survival benefit is considered limited (only 5.5% answered this), the importance of digitalis in symptom relief and rate control, especially in patients with persistent symptoms despite guideline-directed therapies, remains clear.
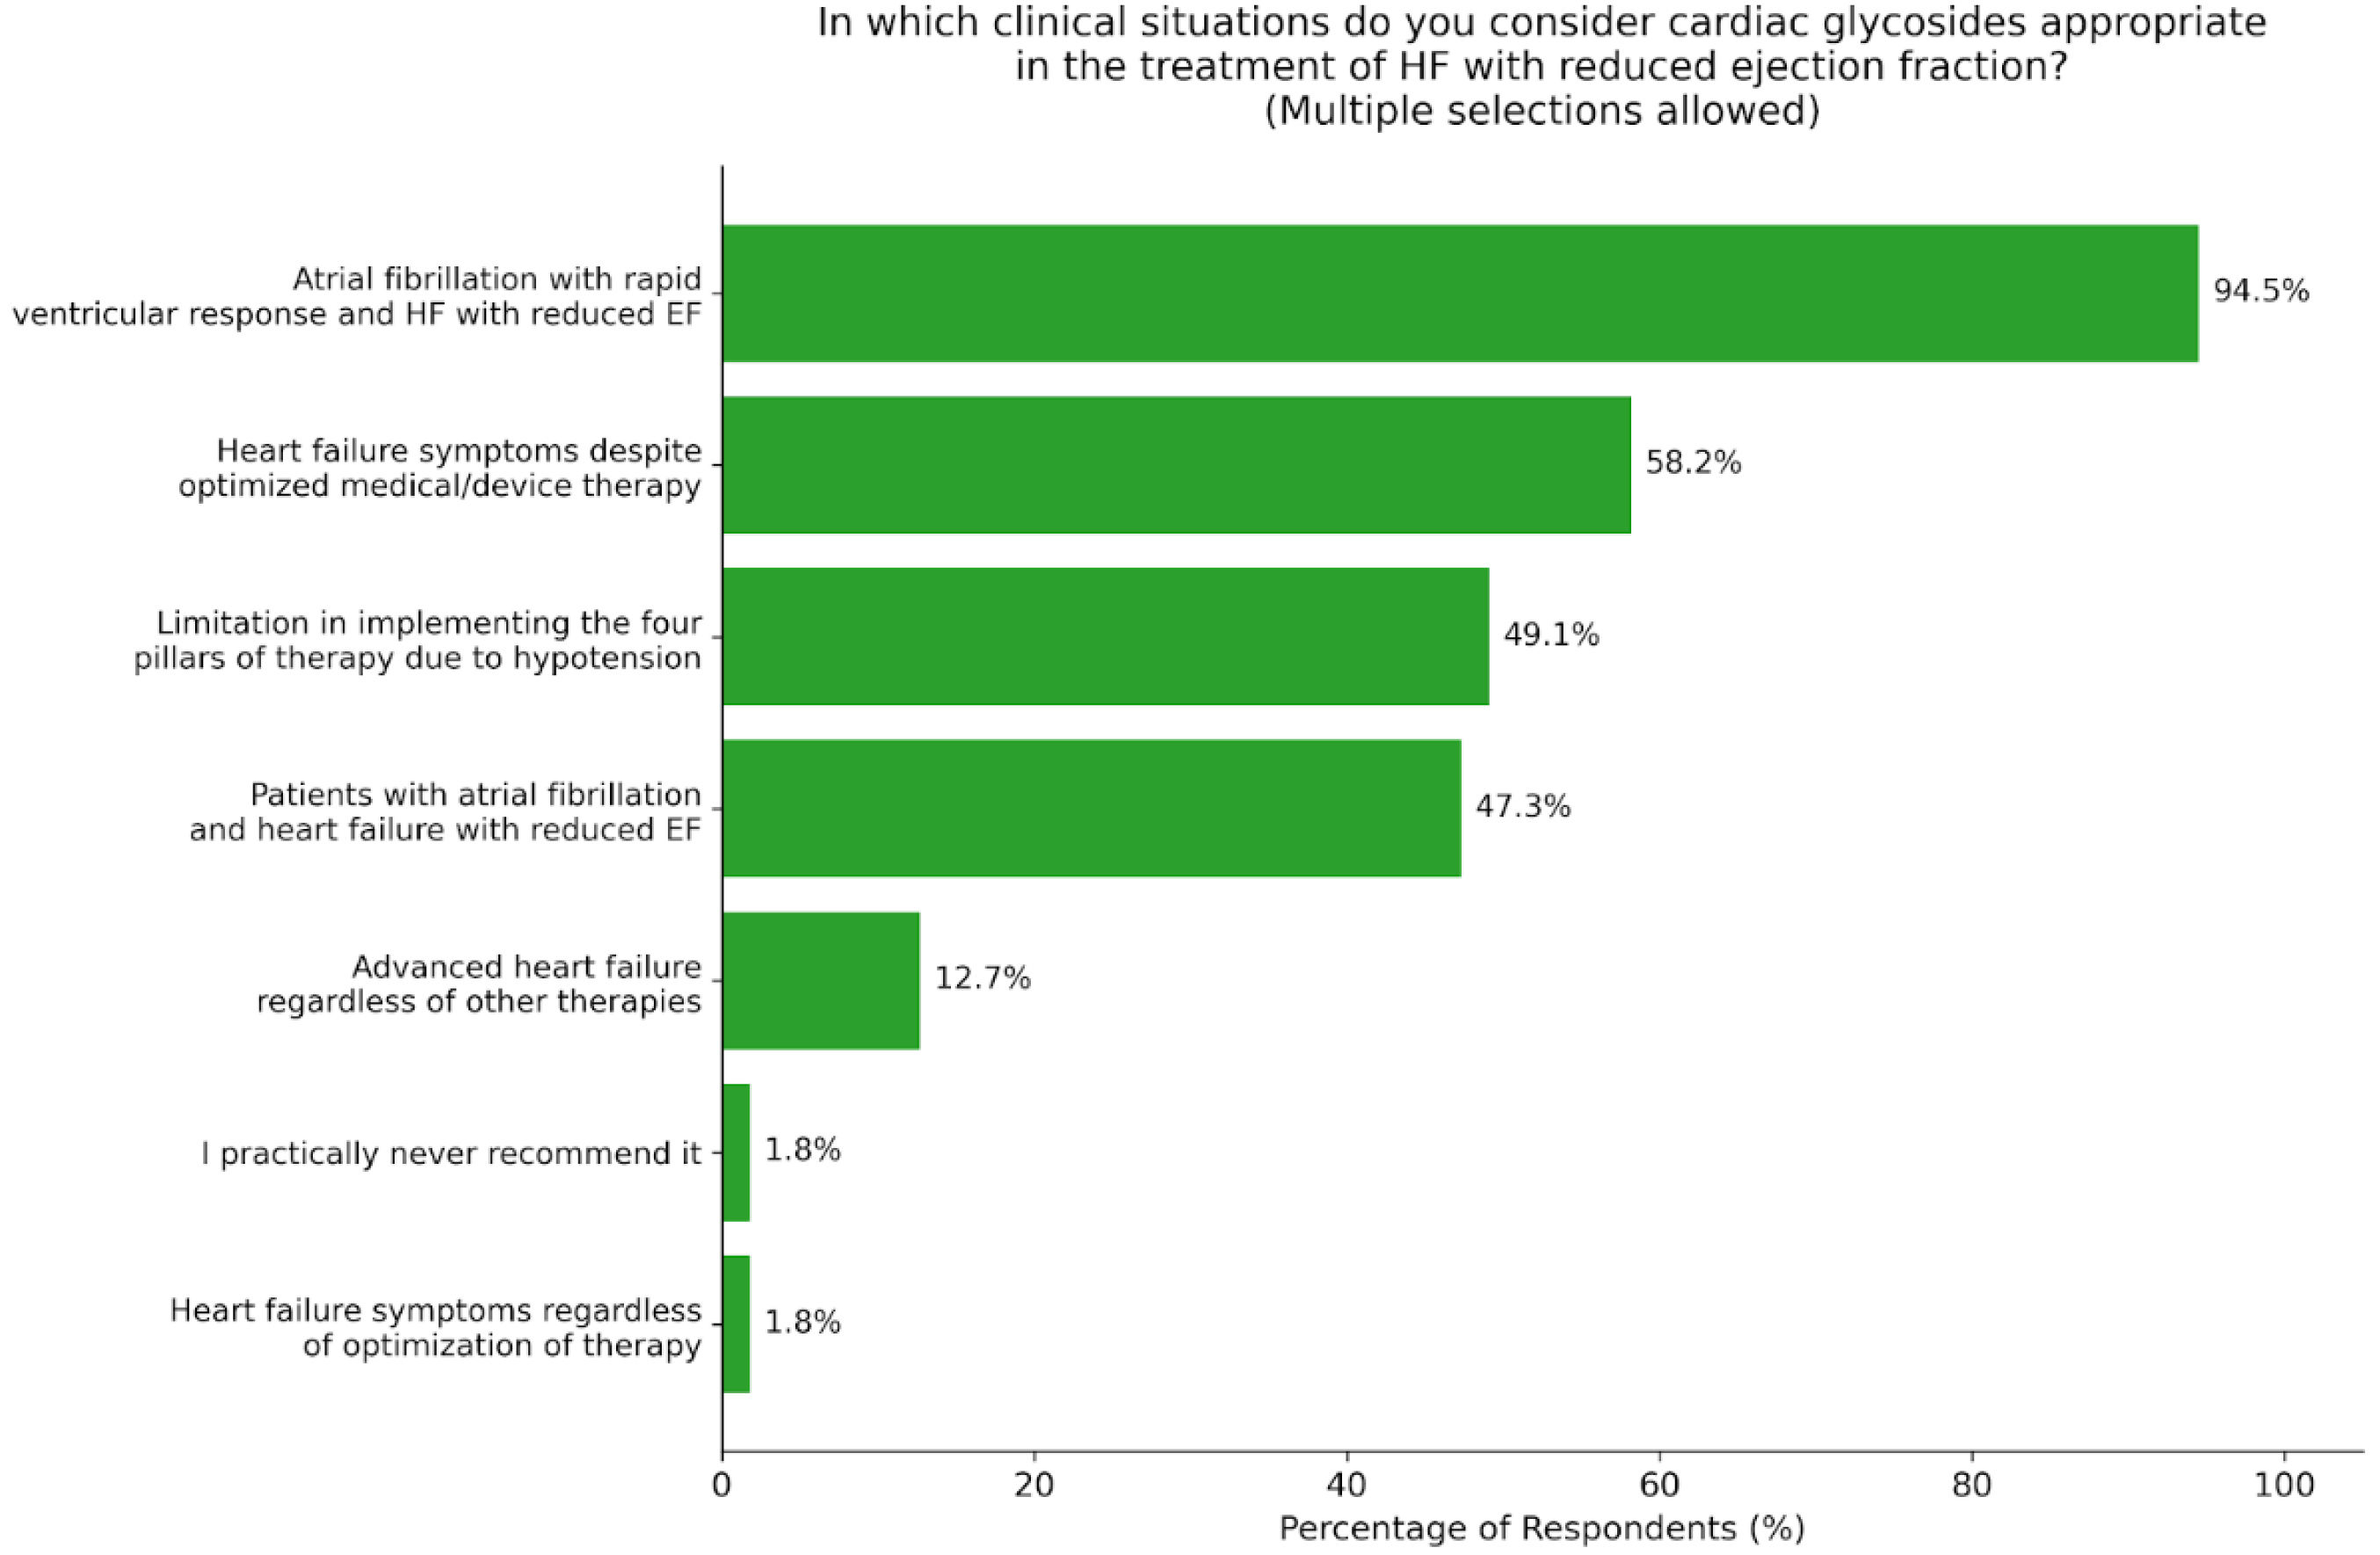
In accordance with this (Figure 7), most respondents (94.5%) endorse glycoside use particularly in patients with AF and rapid ventricular response. A substantial proportion (58.2%) prescribe glycosides to patients with persistent HF symptoms despite optimized medical and device therapies. Additionally, nearly half of the specialists (49.1%) consider cardiac glycosides appropriate when hypotension limits the use of the four foundational HF therapies, reinforcing their utility in complex clinical contexts where standard agents cannot be fully implemented. The role of glycosides in advanced HF also remains relevant, albeit less frequently cited (12.7%), reflecting their position as an adjunctive therapy.
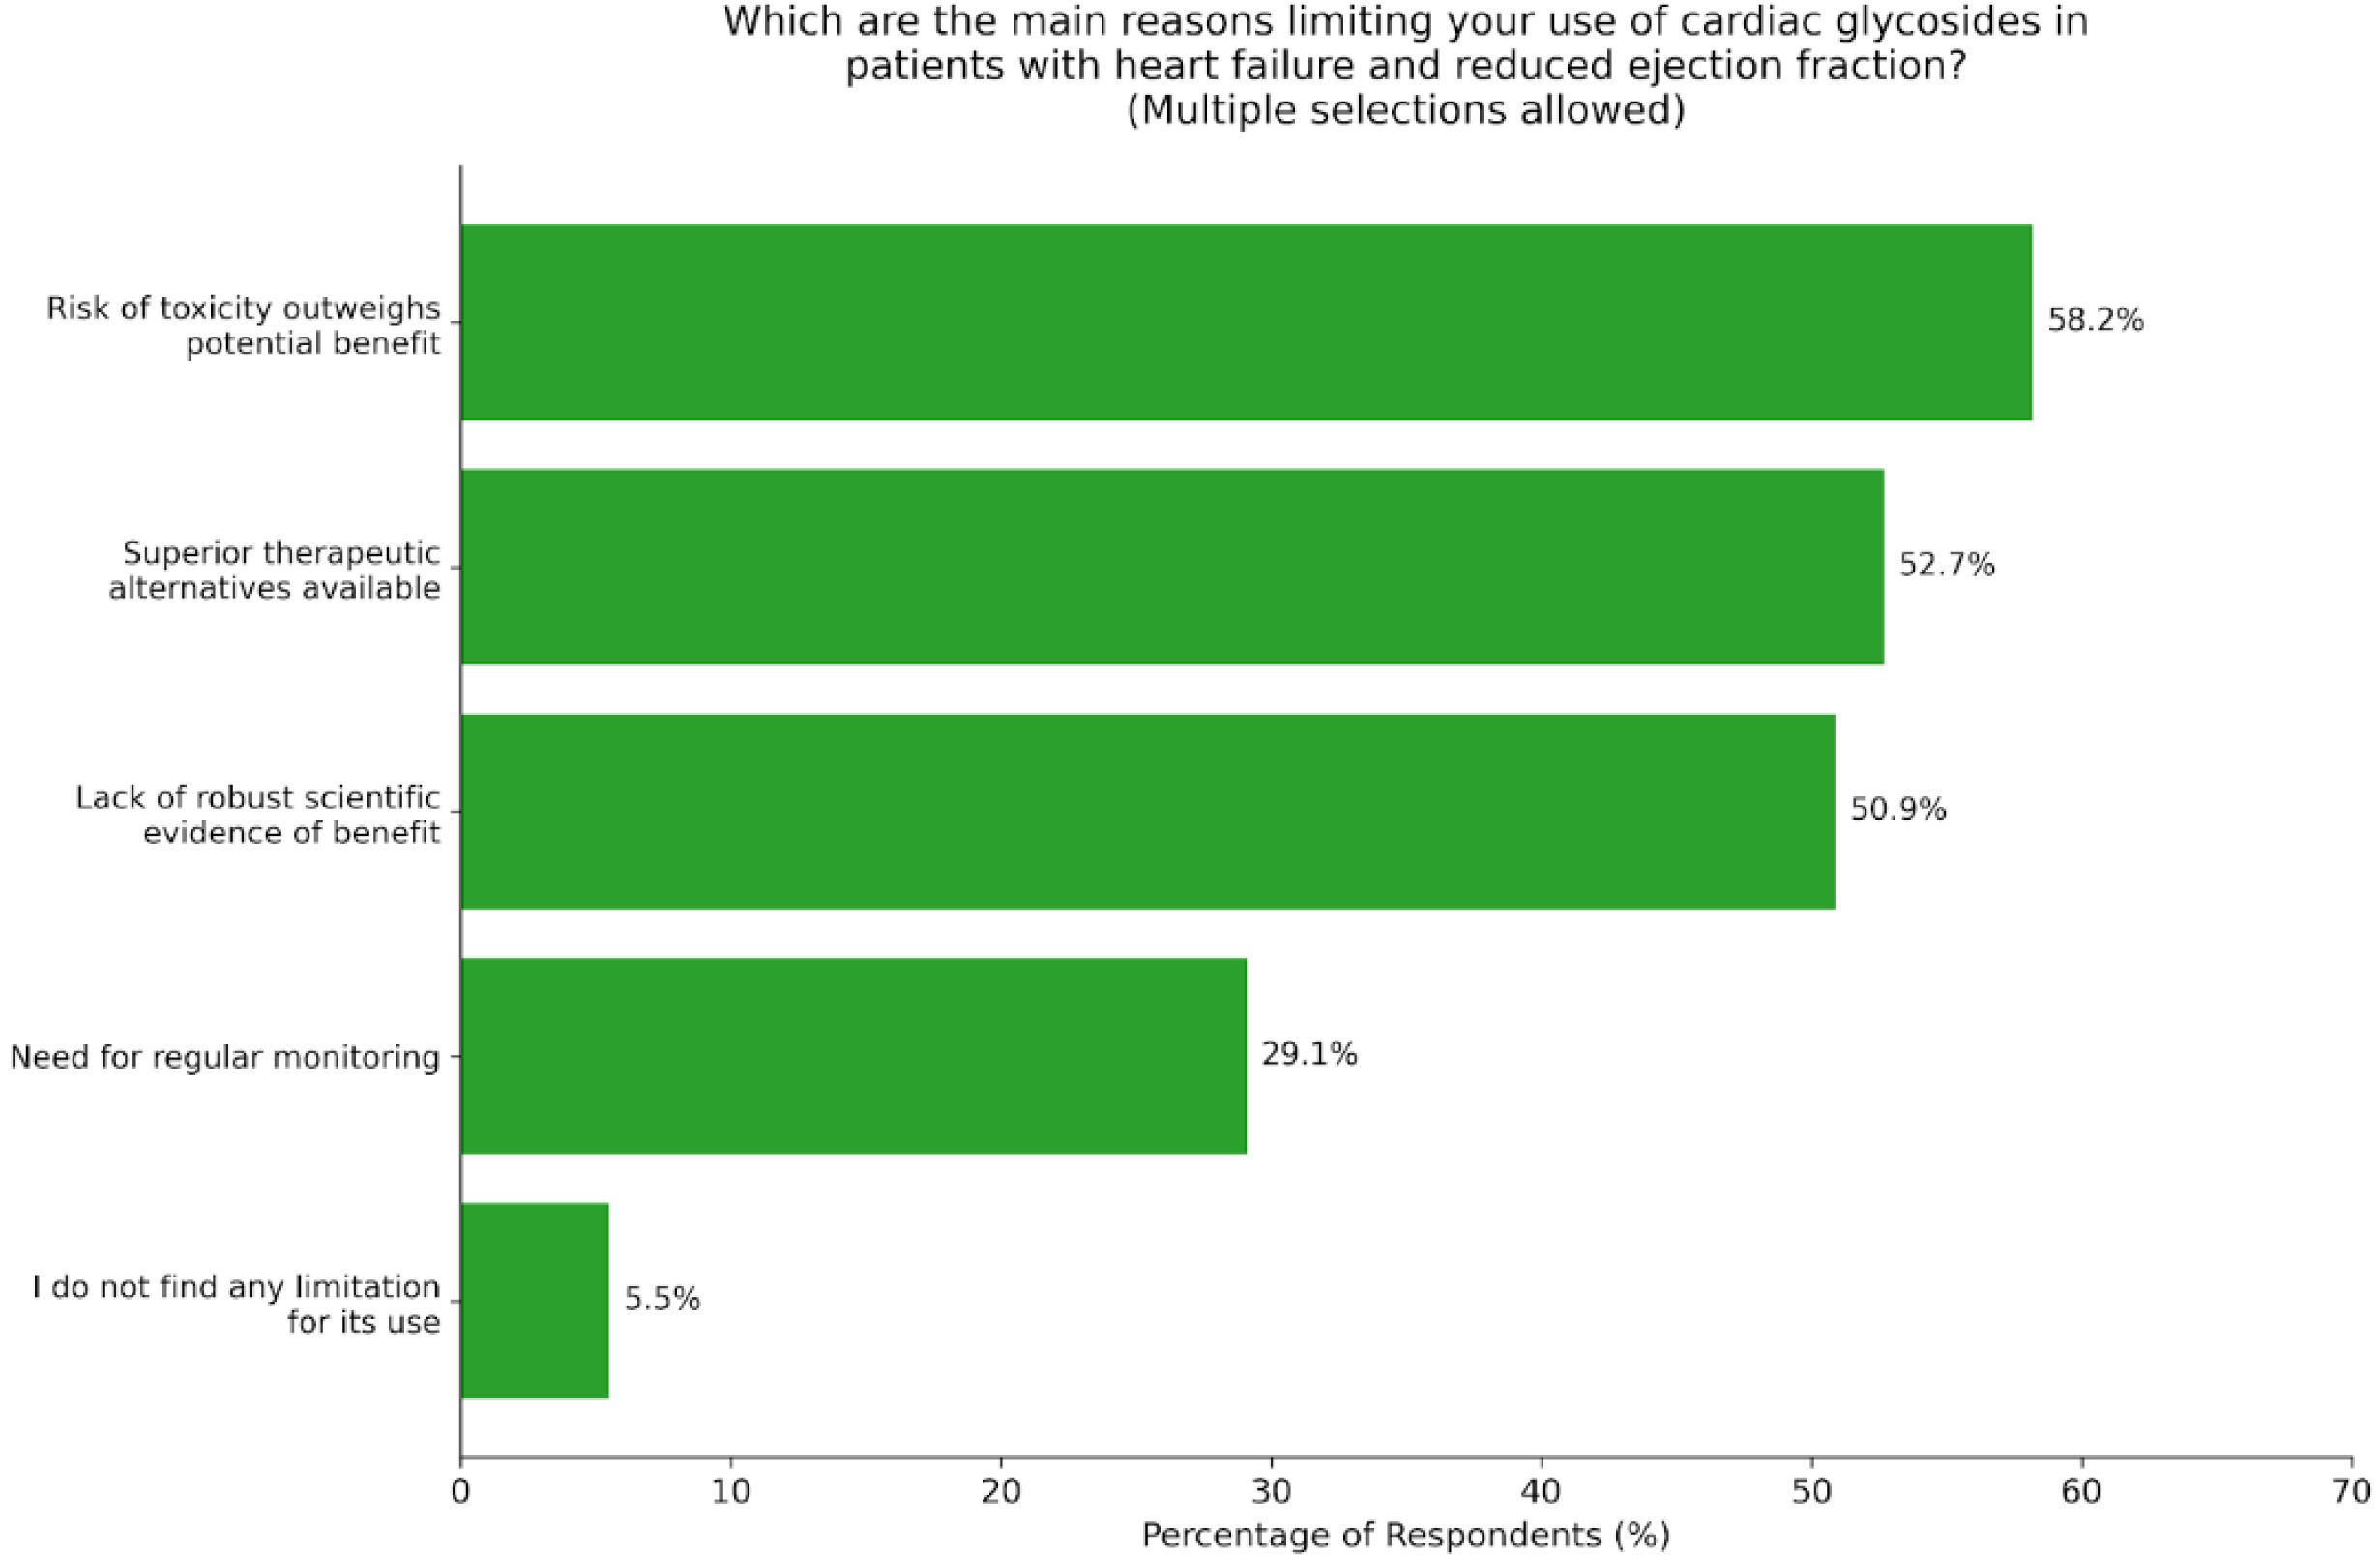
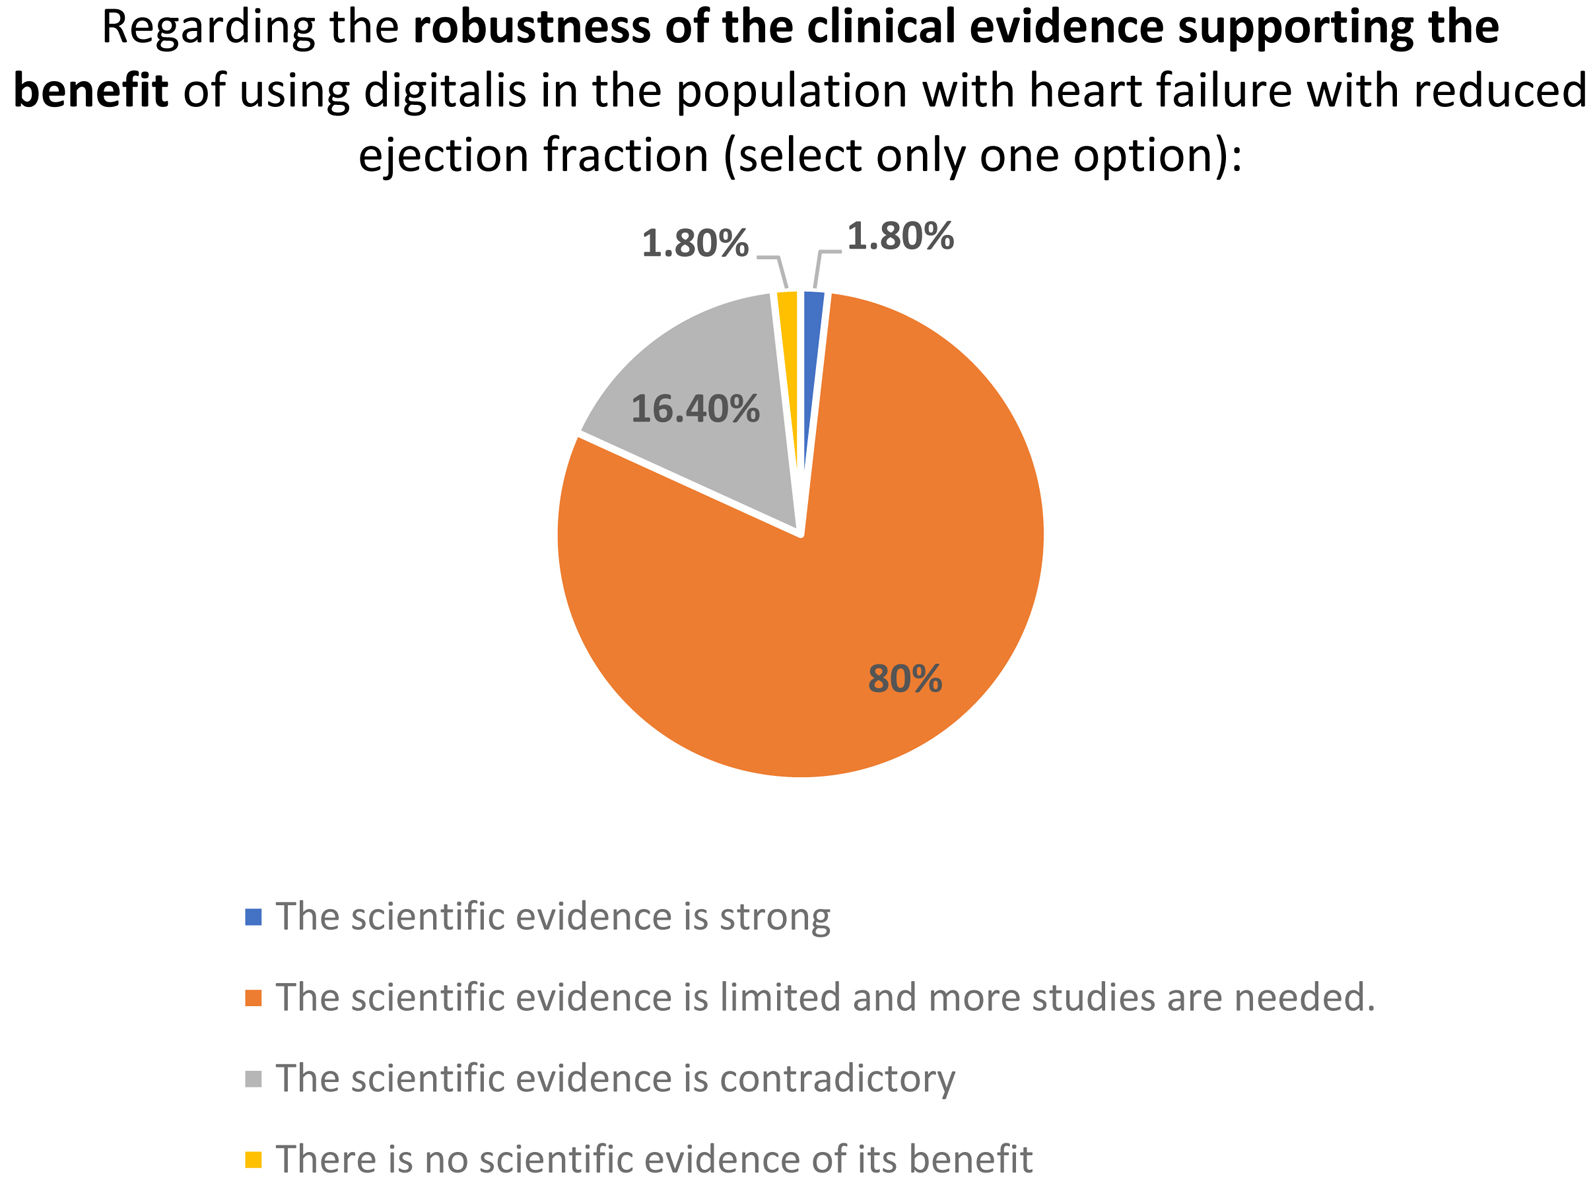
Regarding key barriers to its use (Figure 8), the most cited limitation was the risk of toxicity outweighing benefits (58.2%), reflecting the narrow therapeutic window and historical concerns over toxic levels associated with adverse outcomes. Nearly equivalent proportions highlighted superior therapeutic alternatives (52.7%) and lack of robust scientific evidence (50.9%), underscoring how foundational therapies like ARNI, β-blockers, MRA, and SGLT2i have shifted glycosides to adjunctive roles despite recent trials like DIGIT-HF demonstrating benefit. Notably, 80% of the respondents highlighted the crucial relevance of more studies in this field (Figure 9).
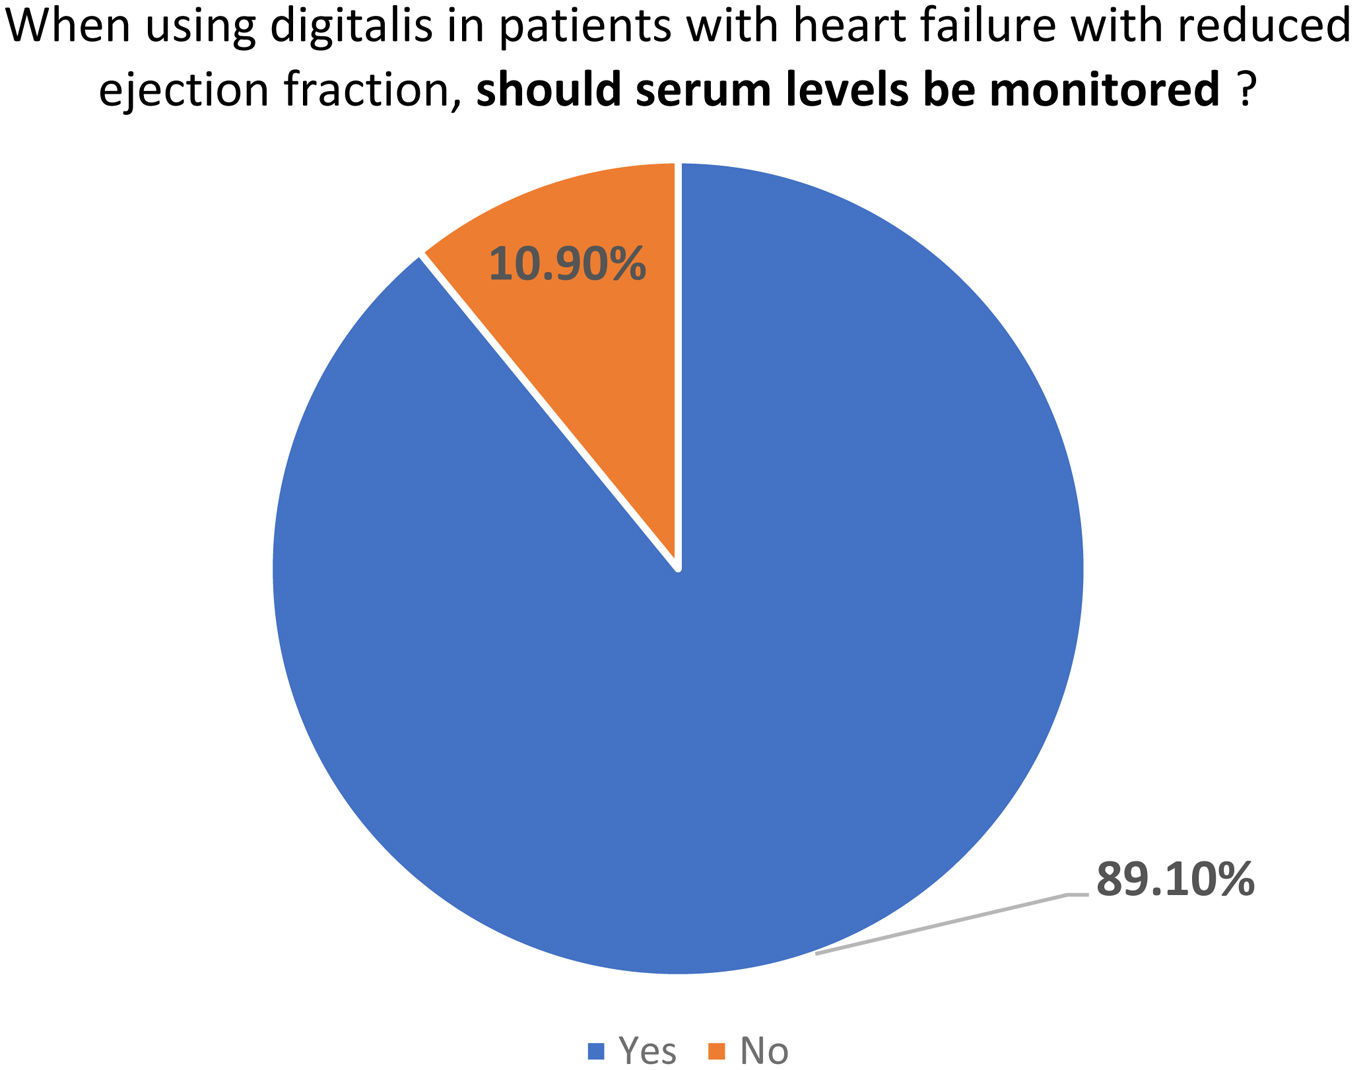
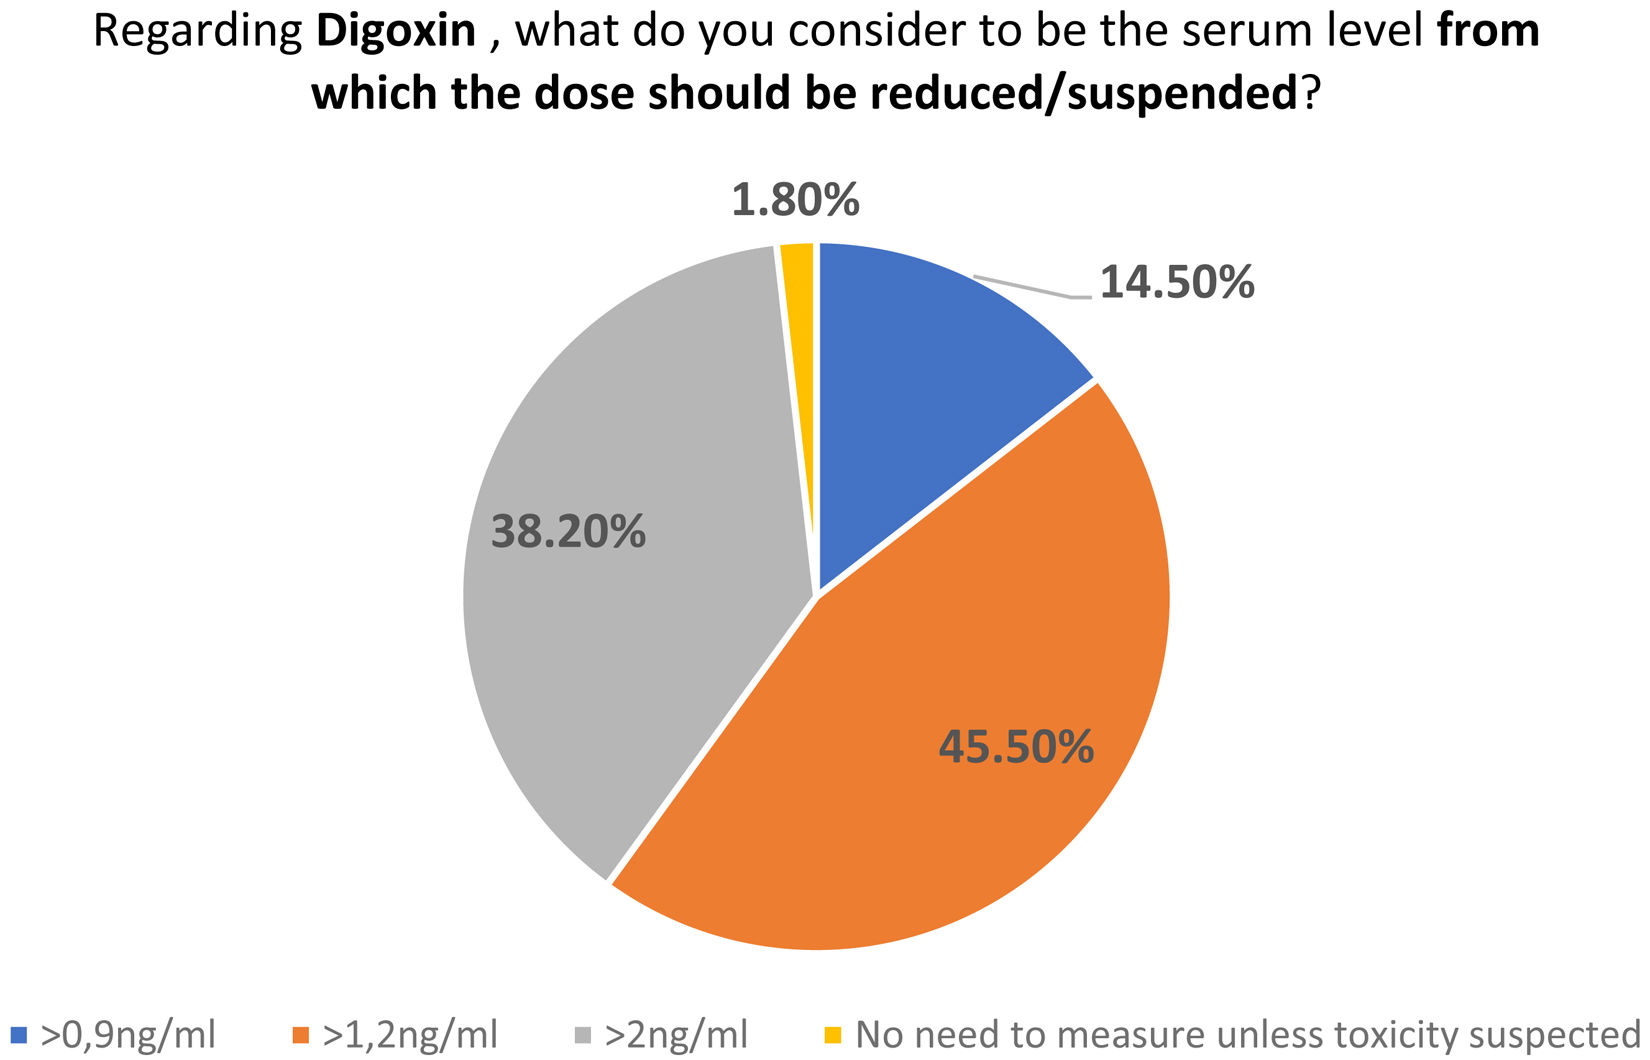
Most specialists actively monitor digitalis levels (Figure 10). Notably, Figure 11 reveals a critical practice-evidence gap: while contemporary data support targeting serum digoxin levels of 0.5–0.9 ng/mL to maximize neurohormonal benefits while minimizing arrhythmic risk, 38% of Portuguese experts only consider dose reduction at >2.0 ng/mL and 45% at >1.2 ng/mL, indicating substantial variability in current clinical practice regarding concentration-guided dosing.
As a limitation of the survey, although it was disseminated to all HF representatives across Portuguese Cardiology centres via heads of their HF services, the anonymity of responses and lack of data on respondents’ institutions preclude definitive assessment of representativeness.
This national survey demonstrates that cardiac glycosides retain a niche but active role in Portuguese HF with reduced ejection fraction patient management, primarily as add-on therapy post-guideline-directed medical therapy, though stronger evidence on safety and efficacy remains a priority.
ConclusionsIn summary, this review reaffirms the continuous, albeit selective, role of digitalis glycosides in contemporary HF with reduced ejection fraction management, bridging historical foundations with modern evidence from trials like DIGIT-HF that demonstrate reduced hospitalizations and mortality when added to guideline-directed therapy. Portuguese specialists’ survey responses highlight pragmatic use primarily for rate control in AF and persistent symptoms, tempered by toxicity concerns and calls for further research. As foundational therapies evolve, low-dose, monitored digitalis offers a cost-effective adjunct for high-risk patients, warranting guideline updates and trials like DECISION to solidify its rediscovered use.
FundingNo funding to declare regarding this article.
Conflicts of interestBoth the first (AVG) and second authors (RC) contributed equally to this article and share first authorship.
AVG: Received honoraria for lectures, presentations, speakers’ bureaus or educational events from AstraZeneca, Bayer, Bial, Boehringer Ingelheim-Lilly, Daiichi Sankyo, Novartis and Takeda.
RC, AF, TPS, NC: nothing to declare.



