




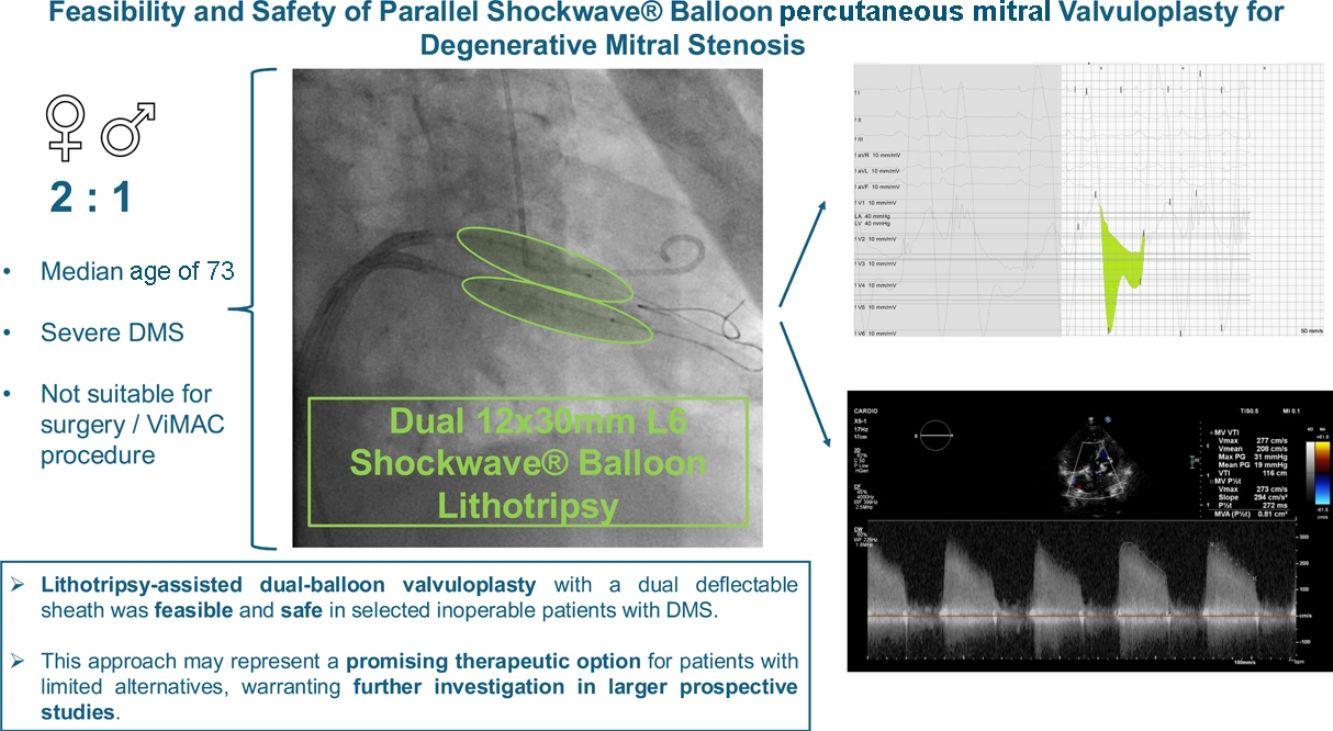
Degenerative mitral valve stenosis (DMS) associated with mitral annular calcification (MAC) poses significant diagnostic and therapeutic challenges. Surgical treatment and conventional percutaneous mitral commissurotomy are often contraindicated, and alternative transcatheter options remain limited and associated with high morbidity and mortality. Lithotripsy-assisted balloon valvuloplasty has recently emerged as a novel percutaneous strategy for selected patients. The objective of this article is to report on an initial feasibility and safety experience of lithotripsy-assisted balloon valvuloplasty without the use of noncompliant balloon post-dilatation.
MethodsWe conducted a prospective, single-center study including consecutive patients with symptomatic severe DMS deemed unsuitable for surgery who underwent lithotripsy-assisted balloon valvuloplasty between August and October 2025. The cases were performed under conscious sedation using intracardiac echocardiography guidance. The procedure consisted of a single transseptal puncture accommodating two deflectable sheaths and simultaneous dual-balloon intravascular lithotripsy, without adjunctive noncompliant balloon valvuloplasty. The primary endpoint was technical success according to the Mitral Valve Academic Research Consortium criteria. Safety endpoints included 30-day major procedure-related morbidity and mortality.
ResultsThree patients (median age 73 years; 67% female) underwent lithotripsy-assisted balloon valvuloplasty. Median baseline noninvasive and invasive transmitral mean gradients were 16 mmHg and 11 mmHg, respectively, decreasing to 7 mmHg after lithotripsy-assisted balloon valvuloplasty. No worsening of baseline mitral regurgitation was observed. There were no major periprocedural complications; one patient experienced a transient, self-limited period of junctional rhythm.
ConclusionsThis proof-of-concept study of lithotripsy-assisted balloon valvuloplasty using a dual deflectable sheath, dual-balloon lithotripsy strategy was feasible and safe in selected patients with DMS. This approach may represent a promising therapeutic option for patients with limited alternatives, warranting further investigation in larger prospective studies.
A estenose mitral degenerativa (DMS) associada a calcificação do anel mitral (MAC) constitui um desafio significativo do ponto de vista diagnóstico e terapêutico. O tratamento cirúrgico e a comissurotomia mitral convencional estão frequentemente contraindicados, e as alternativas percutâneas permanecem limitadas, associando-se a elevada morbilidade e mortalidade. A valvuloplastia mitral com balão assistida por litotrícia (LABV) emergiu recentemente como uma estratégia percutânea inovadora em doentes selecionados. O presente trabalho tem como objetivo descrever os resultados dos primeiros casos de LABV realizados num único centro, sem recurso a balões convencionais de valvuloplastia.
MétodosRealizámos um estudo prospetivo, unicêntrico, incluindo todos os doentes com DMS grave sintomática, considerados não elegíveis para cirurgia ou procedimento valve-in-MAC, submetidos a LABV entre agosto e outubro de 2025. Todos os procedimentos foram efetuados sob sedação, com orientação por ecocardiografia intracardíaca. A técnica consistiu numa única punção transeptal, permitindo a introdução de duas bainhas dirigíveis e a realização de litotrícia intravascular com dois balões em simultâneo, sem valvuloplastia adicional com balões convencionais. O endpoint primário foi o sucesso técnico, definido acordo com os critérios do Mitral Valve Academic Research Consortium. Os endpoints de segurança incluíram morbilidade e mortalidade major relacionadas com o procedimento aos 30 dias.
ResultadosForam incluídos três doentes (idade mediana 73 anos; 67% do sexo feminino). Os gradientes médios transmitrais não invasivos e invasivos basais foram de 16 mmHg e 11 mmHg, respetivamente, reduzindo para 7 mmHg após LABV. Não se verificou agravamento da regurgitação mitral. Não ocorreram complicações major; um doente apresentou um período autolimitado de ritmo juncional.
ConclusõesA técnica de LABV com uma estratégia de duas bainhas dirigíveis e dois balões de litotrícia em paralelo foi eficaz e segura em doentes selecionados com DMS inoperável, com melhoria hemodinâmica aguda significativa e ausência de agravamento da regurgitação mitral. Esta abordagem poderá constituir uma opção terapêutica promissora neste grupo de doentes, devendo estes resultados ser validados em estudos prospetivos de maior dimensão.

Degenerative mitral valve stenosis (DMS) is a complex condition that presents significant challenges in both diagnosis and treatment. It is most commonly associated with mitral annular calcification (MAC), which can extend to the mitral leaflets and subvalvular apparatus. The occurrence of MAC is associated with several atherosclerotic risk factors, including advanced age, female sex, diabetes, smoking, obesity, and chronic kidney disease.1 The reported incidence of MAC varies widely depending on both the age of the population studied and the imaging modality used, occurring in approximately 10% of individuals older than 60 years and increasing to about one-third of those over 90 years.2
Although MAC-related mitral valve dysfunction is the most common complication, moderate to severe mitral regurgitation (MR) is the predominant manifestation, occurring in up to 30% of patients with MAC.1,3 In contrast, significant MS is much less frequent, affecting approximately 8% of patients.1,3 Its pathophysiology differs significantly from that of rheumatic mitral stenosis. Rheumatic disease is characterized by commissural fusion, leaflet thickening and chordal involvement, resulting in a “funnel-shaped” orifice.4 In contrast, DMS is driven by extensive annular and basal leaflet calcification, producing a “tunnel-like” obstruction that usually spares leaflet tips and lacks commissural fusion.4 Consequently, conventional echocardiographic parameters, particularly mitral valve area by planimetry, are less reliable in this setting, and standard interventions such as percutaneous balloon commissurotomy are generally not suitable.5
Because DMS primarily affects elderly patients with multiple comorbidities, surgical intervention is often associated with high operative risk and increased morbidity. Current European Society of Cardiology/European Association for Cardio-Thoracic Surgery Guidelines on Valvular Heart Disease state that transcatheter mitral valve implantation can be considered in highly selected patients with severe MV dysfunction and extensive MAC, provided the procedure is performed in experienced centers.6 Nevertheless, reported outcomes remain suboptimal, with one-year mortality ranging from 10 to 30% even after successful treatment.6 Some patients are not candidates for this therapy due to anatomical features that suggest a high risk of embolization or left ventricular outflow tract (LVOT) obstruction. Together, the limited effectiveness of established therapies and the lack of strong randomized data highlight a significant unmet clinical need in this population.
Lithotripsy-assisted balloon valvuloplasty has recently emerged as a novel percutaneous technique for treating calcific mitral stenosis. Since the first in-human report in 2019,7 small case series have described encouraging short-term clinical and hemodynamic results, demonstrating meaningful reductions in transmitral gradients (TMG) without significant worsening of concomitant MR.8–12
Technical refinements of lithotripsy-assisted balloon valvuloplasty have gradually overcome key procedural limitations, particularly challenges related to stable device positioning and adequate contact with heavily calcified mitral structures, which are essential for effective lithotripsy delivery. The introduction of larger-diameter lithotripsy balloons was instrumental in resolving these issues. Recent case reports have described the use of peripheral 12-mm Shockwave® balloons, which are compatible with 0.018″ support guidewires and deliver two lithotripsy pulses per second, thereby streamlining the procedure.8,13,14 In addition, a dual deflectable sheath strategy has recently been proposed to improve catheter stability and enhance the precision of lithotripsy balloon positioning across the mitral valve.13 At the same time, Giustino et al. reported a small case series using a triple-balloon configuration, which resulted in significant hemodynamic improvement and removed the need for adjunctive noncompliant balloon dilation.14
ObjectivesThe aim of our work is to report the feasibility and safety of the first lithotripsy-assisted balloon valvuloplasty cases performed in our center, using a dual deflectable sheath strategy with simultaneous dual-balloon lithotripsy, without adjunctive noncompliant balloon valvuloplasty.
MethodsStudy design and populationWe performed a prospective, single-center study including consecutive patients treated between August and October 2025 for symptomatic severe DMS. Eligible patients had a predominant mitral stenosis phenotype with significant calcification of the mitral leaflets and/or subvalvular apparatus (defined by a Wilkins score >8), considered predictive of poor outcomes with conventional percutaneous balloon mitral valvuloplasty. All patients underwent comprehensive preprocedural screening with cardiac computed tomography. Patients were deemed at high risk for transcatheter mitral valve replacement (TMVR) due to either an increased likelihood of prosthesis non-anchoring in valve-in-MAC (MAC score ≤6) or a high risk of LVOT obstruction (predicted neo-LVOT <120 mm2). In addition, all patients were considered unsuitable for surgical intervention because of prohibitive surgical risk or surgical refusal due to significant comorbidities, as determined during a multidisciplinary heart team discussion. Patients were therefore scheduled to undergo lithotripsy-assisted balloon valvuloplasty. Its use was off-label, and written informed consent was obtained from all patients prior to the procedure.
Procedural protocolAll procedures were conducted in the cardiac catheterization laboratory by a dedicated structural intervention team, comprising two interventional cardiologists, two technicians and two nurses. Procedures were performed under conscious sedation, without the need for general anesthesia or endotracheal intubation.
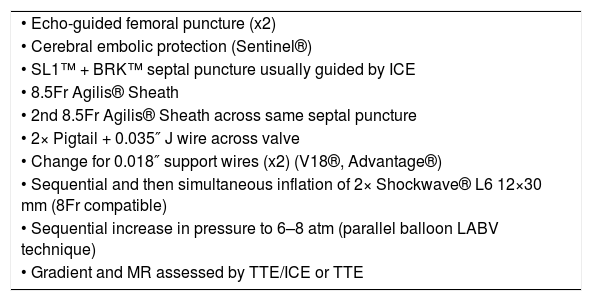
The procedure was performed as described (Table 1):
- 1.
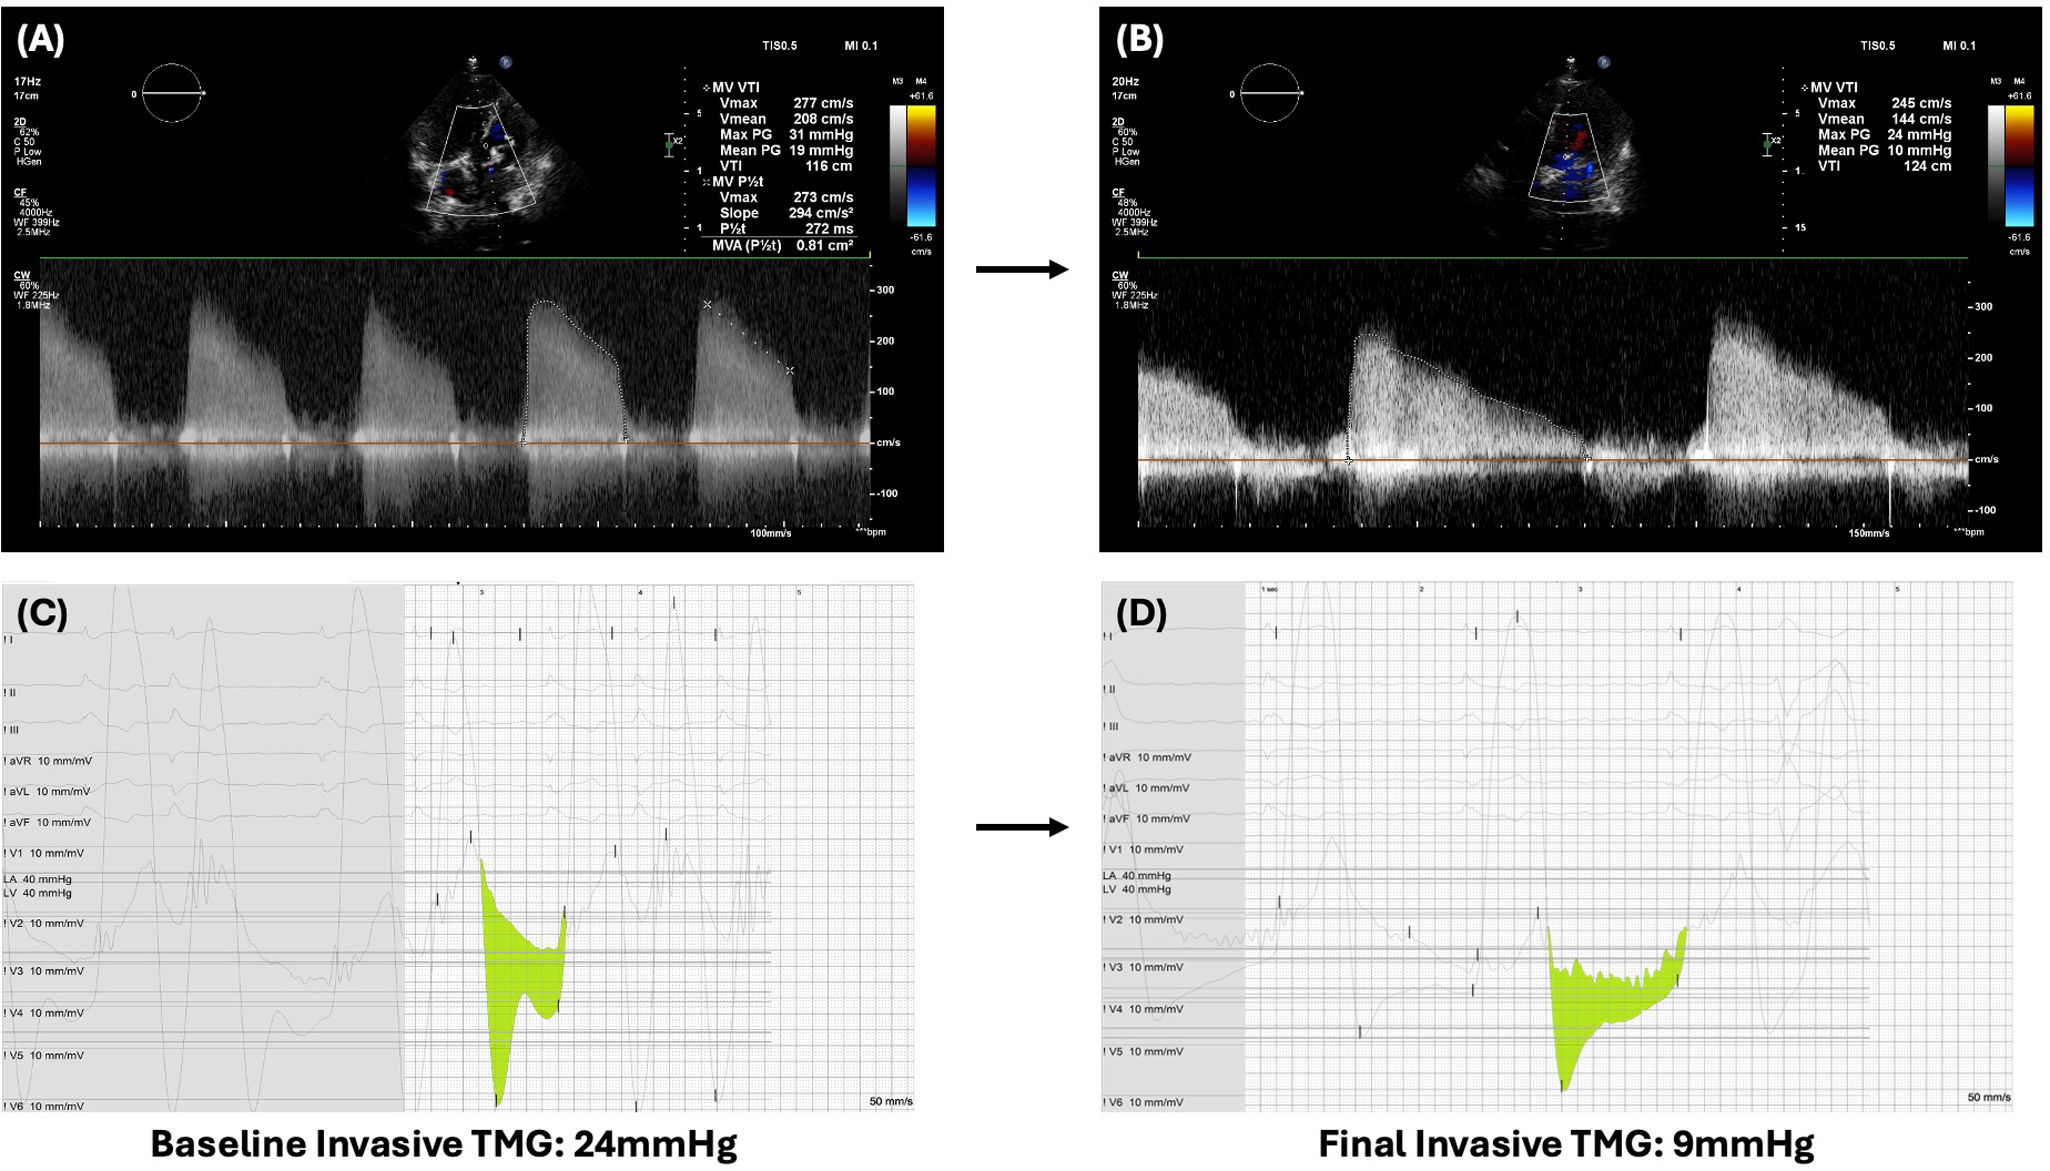
Preprocedural transthoracic echocardiography for evaluation of noninvasive TMG, estimated MV area and baseline MR – Figure 1A and C;
- 2.
Establishment of two radial arterial and two ultrasound-guided venous femoral accesses. Deployment of a cerebral embolic protection device (CEPD) – Sentinel™ (Boston Scientific®) – and a pigtail catheter through the arterial accesses. Progression of an intracardiac echocardiography (ICE) probe – ACUSON AcuNav™ (Johnson & Johnson®) and an over-the-wire SL1™ sheath to the right atrium;
- 3.
ICE-guided transseptal puncture with a BRK™ needle (Abbott®) – Figure 2A. Over-the-wire progression of two steerable 8.5 French Agilis™ sheaths (Abbott®) through the same puncture – Figure 2B. Progression of two pigtail catheters to the left atrium and a 0.035″ J wire through the mitral valve. Invasive assessment of left atrial pressures (LAP), left ventricular (LV) pressures and TMG;
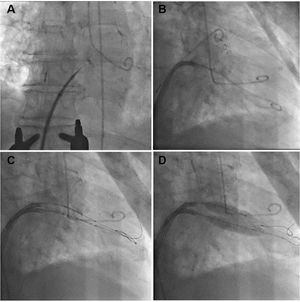 Figure 2.
Fluoroscopy images of lithotripsy-assisted balloon valvuloplasty – (A) transseptal puncture; (B) progression of first Agilis™ steerable sheath; (C) delivery of two peripheral lithotripsy 12×30 mm Shockwave® balloons over V18™ guidewires through two Agilis™ steerable sheaths; (D) simultaneous balloon inflation with lithotripsy pulse delivery.
- 4.
Exchange of pigtail catheters by two 0.018″ support guidewires (Boston Scientific® V18™/Terumo® Glidewire Advantage®). Over-the-wire delivery of two 12×30 mm Shockwave® L6 balloons – Figure 2C;
- 5.
Sequential and then simultaneous balloon inflations with lithotripsy delivery (30 pulses per cycle; maximum 600 pulses) without ventricular pacing – Figure 2D. Sequential increase in balloon inflation pressure (6–8 atm);
- 6.
Assessment of final invasive LAP, invasive and noninvasive TMG and MR – Figure 1B and D;
- 7.
Retrieval of CEPD and access closure.


Protocol for lithotripsy-assisted balloon valvuloplasty.
| • Echo-guided femoral puncture (x2) |
| • Cerebral embolic protection (Sentinel®) |
| • SL1™ + BRK™ septal puncture usually guided by ICE |
| • 8.5Fr Agilis® Sheath |
| • 2nd 8.5Fr Agilis® Sheath across same septal puncture |
| • 2× Pigtail + 0.035″ J wire across valve |
| • Change for 0.018″ support wires (x2) (V18®, Advantage®) |
| • Sequential and then simultaneous inflation of 2× Shockwave® L6 12×30 mm (8Fr compatible) |
| • Sequential increase in pressure to 6–8 atm (parallel balloon LABV technique) |
| • Gradient and MR assessed by TTE/ICE or TTE |
Fr: French; ICE: intracardiac echocardiography; TEE: transesophageal echocardiography; TTE: transthoracic echocardiography.
The primary endpoint of the study was technical success, defined according to the Mitral Valve Academic Research Consortium Consensus Document15 as absence of procedural mortality; successful access, delivery, and retrieval of the devices; successful deployment and correct positioning of the devices; and freedom from emergency surgery or reintervention related to the device or access procedure.
Regarding the safety endpoints, procedure-related morbidity and mortality were assessed at 30 days, including death; stroke/systemic embolism; life-threatening bleeding; major vascular complications; major cardiac structural complications; severe hypotension, heart failure or respiratory failure requiring intravenous pressors or invasive or mechanical heart failure treatments; and any valve-related dysfunction requiring urgent surgery or repeat intervention.
Secondary efficacy endpoints included acute hemodynamic efficacy, which was defined as a reduction in TMG >5 mmHg; improvement in MV area (when measurable by echocardiography), and any change in the severity of baseline MR. Minor complications were also assessed as secondary safety endpoints.
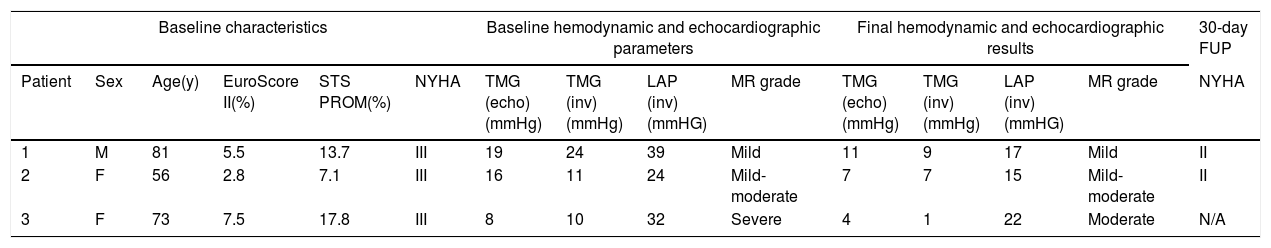
ResultsBaseline characteristicsThree patients underwent lithotripsy-assisted balloon valvuloplasty during the study period. Median age was 73 years, and two patients (67%) were female (Table 2). All patients were classified as NYHA class III, and the median EuroSCORE II and STS scores were 5.52% and 13.7%, respectively (Table 2). One patient was declined surgery due to a porcelain aorta, and two were declined due to advanced age and multiple comorbidities. All patients presented with extensive mitral annular and leaflet calcification and were considered unsuitable for valve-in-MAC TMVR due to a prohibitive predicted risk of LV outflow tract obstruction.
Clinical, hemodynamic and echocardiographic parameters in all patients before and after lithotripsy-assisted balloon valvuloplasty.
| Baseline characteristics | Baseline hemodynamic and echocardiographic parameters | Final hemodynamic and echocardiographic results | 30-day FUP | |||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Patient | Sex | Age(y) | EuroScore II(%) | STS PROM(%) | NYHA | TMG (echo)(mmHg) | TMG (inv)(mmHg) | LAP (inv)(mmHG) | MR grade | TMG (echo)(mmHg) | TMG (inv)(mmHg) | LAP (inv)(mmHG) | MR grade | NYHA |
| 1 | M | 81 | 5.5 | 13.7 | III | 19 | 24 | 39 | Mild | 11 | 9 | 17 | Mild | II |
| 2 | F | 56 | 2.8 | 7.1 | III | 16 | 11 | 24 | Mild-moderate | 7 | 7 | 15 | Mild-moderate | II |
| 3 | F | 73 | 7.5 | 17.8 | III | 8 | 10 | 32 | Severe | 4 | 1 | 22 | Moderate | N/A |
F: female; FUP: follow-up; LAP: left atrial pressure; M: male; MR: mitral regurgitation; NYHA: New York Heart Association; STS PROM: Society of Thoracic Surgeons Predicted Risk of Mortality; TMG: transmitral gradient; y: years.
Median procedural time, radiation dosage and contrast volume were 184 minutes, 415 mGy and 46 mL, respectively.
Median baseline noninvasive and invasive TMG were 16 mmHg and 11 mmHg, respectively, with median LAP of 32 mmHg (Table 2). Following lithotripsy-assisted balloon valvuloplasty, technical success was achieved in all three patients, as well as acute hemodynamic improvement, with a final median noninvasive and invasive TMG of 7 mmHg and median LAP of 17 mmHg (Table 2). Mitral valve area by echocardiographic estimation was obtainable in one case, increasing from 0.81 cm2 to 1.00 cm2. No patient exhibited worsening of baseline MR severity.
No major procedure-related complications occurred. In all three cases, following retrieval of the CEPD, no macroscopic debris was observed. One patient required transient temporary transvenous pacing due to a self-limited period of junctional rhythm following a lithotripsy cycle.
At the 30-day follow-up, improvement in NYHA functional class was observed in two patients, both improving from class III to class II. One patient required hospitalization at 30 days due to a respiratory infection and subsequently died; this event was adjudicated as non-procedure-related.
DiscussionThis series adds to the limited but growing body of evidence supporting lithotripsy-assisted balloon valvuloplasty as a potential treatment option for patients with DMS and extensive calcification who are not candidates for surgery or conventional transcatheter therapies. To our knowledge, this represents the first reported national case series using this strategy.
The procedural concept aligns with previously described lithotripsy-based mitral interventions, while incorporating important technical adaptations. Prior reports have demonstrated the feasibility of multi-balloon lithotripsy configurations8–11 and, more recently, the use of a dual steerable sheath strategy to optimize device positioning and stability across the mitral valve.13 Our approach combines dual deflectable sheath support through a single transseptal puncture with simultaneous dual-balloon lithotripsy delivery, while avoiding adjunctive high-pressure noncompliant balloon valvuloplasty. This modification simplifies the procedural workflow and may reduce mechanical trauma to the valve apparatus.
Consistent with previous reports, we observed significant acute hemodynamic improvement with meaningful reductions in TMG without clinically relevant increases in MR. Nevertheless, the final gradient remained within the range compatible with significant stenosis, which might be expected in DMS associated with extensive MAC. Unlike rheumatic disease, in which commissural fusion can be effectively relieved by balloon commissurotomy, the obstructive substrate in DMS frequently involves circumferential annular calcification and basal leaflet rigidity, creating a relatively fixed inflow tunnel.
The mechanism underlying the observed reduction in gradient is likely multifactorial. Intravascular lithotripsy generates acoustic pressure waves that selectively induce microfractures in calcified structures while sparing surrounding soft tissue. In a study of cadaveric hearts, micro-CT demonstrated these microfractures,16 which may reduce radial stiffness of the annulus and basal leaflet segments, improve leaflet excursion, and increase effective orifice area modestly. However, because the calcified structures are not removed and the anatomical obstruction is often extensive, complete normalization of TMG is unlikely.
In this context, the primary therapeutic goal of lithotripsy-mediated calcium modification is not necessarily to completely normalize TMG, but rather to achieve a meaningful reduction in the gradient, improvement in LAP, and/or relief of symptoms, while minimizing the risk of severe MR or major procedural complications. Accordingly, once we achieved satisfactory hemodynamic improvement in our series, we avoided high-pressure balloon dilation, which may have reduced the risk of structural leaflet injury.
Compared to previous reports, we used relatively large-diameter lithotripsy balloons, which may improve circumferential contact with the calcified annulus and basal leaflet segments. This enhances energy delivery and effectiveness while allowing for controlled expansion. This may represent an additional factor contributing to the reduction of the gradient without worsening regurgitation.
From a technical standpoint, several procedural simplifications are worth noting. The entire intervention was performed using a single transseptal puncture to accommodate two steerable sheaths, eliminating the need for a septostomy. Rapid ventricular pacing during balloon inflation was not necessary, which simplified the procedure and reduced its complexity. Additionally, using ICE instead of transesophageal guidance provided precise imaging support while avoiding general anesthesia and endotracheal intubation, which is especially beneficial for elderly and high-risk patients.
Beyond the inherent limitations of the very small sample size and the single-center design, which restrict generalizability, several important knowledge gaps remain. Although lithotripsy-assisted balloon valvuloplasty leads to significant immediate hemodynamic improvement without the need for standard balloon post-dilatation, it remains uncertain whether this benefit can be consistently maintained during short- and long-term follow-up, or if routine or selective post-dilatation with conventional balloons will be necessary to optimize durability. Optimal balloon sizing remains poorly defined, and there are no standardized criteria for selecting the most appropriate dimensions based on individual valve anatomy. Additionally, potential conduction disturbances are an important area of interest. Although only transient pacing requirements were observed in our series, the long-term impact of lithotripsy-assisted balloon valvuloplasty on conduction abnormalities remains unknown. The role of cerebral embolic protection devices also deserves further investigation, as the theoretical risk of embolization caused by calcium fragmentation has not yet been systematically studied.
Future research should prioritize larger prospective studies that use standardized procedural protocols, include systematic multimodal imaging follow-up, and provide extended clinical surveillance. Such investigations are essential to better define the safety profile of lithotripsy-assisted balloon valvuloplasty, optimize procedural strategies, evaluate the durability of hemodynamic improvements, and clarify the overall clinical impact of this emerging technique.
This initial case series demonstrates that lithotripsy-assisted balloon valvuloplasty, using a dual deflectable sheath and dual-balloon strategy, is feasible and procedurally safe in selected inoperable patients with DMS. The technique consistently improved acute hemodynamics without increasing MR or causing major procedural complications, all while avoiding high-pressure balloon dilation and general anesthesia. Although this study is hypothesis-generating due to its small sample size and exploratory nature, the findings suggest that lithotripsy-assisted balloon valvuloplasty may be a promising adjunctive option for anatomically complex patients who lack conventional therapeutic alternatives. These results warrant further evaluation in larger prospective studies.
AuthorshipConception and design of the research: João Silva Marques. Acquisition of data: Daniel Inácio Cazeiro, Diogo Ferreira, Fábio Viveiros, João Silva Marques. Analysis and interpretation of the data: Daniel Inácio Cazeiro, João Silva Marques. Writing of the manuscript: Daniel Inácio Cazeiro, Diogo Ferreira, Fábio Viveiros, João Silva Marques. Critical revision of the manuscript for content: Daniel Inácio Cazeiro, Diogo Ferreira, Fábio Viveiros, Catarina Oliveira, Tiago Rodrigues, Ana Rita Francisco, Cláudia Moreira Jorge, Pedro Cardoso, Fausto J. Pinto, João Silva Marques.
Ethical considerationsWritten informed consent was obtained prior to all the procedures, as well as authorization for use of data for investigation purposes, according to a general clinical protocol validated by the local ethics committee.
Declaration of generative AI and AI-assisted technologies in the writing processChatGPT 5.2 was used for linguistic correction and language refinement. After using this tool, the authors reviewed and edited the content as needed and take full responsibility for the content of the published article.
FundingNo authors received financial support for the research, authorship, and/or publication of this article.
Conflicts of interestThe authors declare no potential conflicts of interest with respect to the research, authorship and/or publication of this article.



